

IDEF0 functional architecture of rehabilitation engineering pedagogy: clinical evaluations and anthropometric user constraints bounded by regulatory standards, operationalized via mechatronic prototyping and sensor-fusion telemetry to yield personalized assistive and neuro-therapeutic solutions.
Rehabilitation Engineering Education, viewed through this diagram, teaches students how to convert human needs into usable technology responsibly. The Inputs keep the focus anchored on the person: functional limitations, daily-life challenges, and clinical observations that reveal what must be improved. The Controls act as guardrails, shaping designs so they fit medical realities—safety, usability, effectiveness, and compliance with accepted rehabilitation pathways. The Mechanisms reflect how learning becomes tangible: workshops, tools, iterative prototyping, and testing practices that train students to move from ideas to working solutions. The Outputs are not only devices, but also the graduate’s capability to design and justify assistive interventions—wheelchair components, orthotic supports, adaptive interfaces, or rehabilitation aids—guided by evidence and evaluated by whether they meaningfully improve real life.
Rehabilitation Engineering is a multidisciplinary field that applies engineering principles to develop technologies and devices that restore, enhance, or support the functional abilities of individuals with physical impairments. Closely linked with Biomedical Engineering, this area draws on advanced tools from fields such as Bioinformatics to tailor assistive technologies to users’ physiological and anatomical profiles. By using insights from Biomaterials, engineers ensure that prosthetics, orthotic supports, and wearable devices are both functional and biocompatible.
Functional movement restoration depends on principles from Biomechanics, enabling the accurate modeling of joint motion, gait, and balance. Complementary techniques from Biomedical Signal Processing facilitate the decoding of muscle signals and the control of exoskeletons or brain-computer interfaces. Advancements in Cardiovascular Engineering inform rehabilitation programs for stroke survivors and patients with chronic heart conditions.
In clinical settings, Clinical Engineering ensures the safety and integration of rehabilitation equipment into patient care workflows. Imaging modalities developed in Medical Imaging are employed to assess progress and monitor muscle or nerve recovery. Cognitive and motor restoration are enhanced through interfaces inspired by Neural Engineering, opening new frontiers in neurorehabilitation.
Pharmaceutical support—developed under Pharmaceutical Engineering—often accompanies physical therapy to aid in pain management and tissue repair. For complex injuries, integration with Tissue Engineering and Regenerative Medicine enables novel solutions like bio-scaffolds or stem-cell infused implants. These cutting-edge treatments are built on a strong foundation in Chemical Engineering, especially when biomaterials or controlled drug delivery systems are involved.
Biological therapies are scaled using principles from Biochemical Engineering, and therapeutic processes are often optimized through Chemical Catalysis and Reaction Engineering. Power-efficient, portable rehabilitation devices benefit from strategies in Chemical Energy Systems Engineering, while new materials for limb supports stem from Chemical Materials Engineering.
Systems integration and reliability testing align with the goals of Chemical Process Engineering. To simulate and improve performance, Computational Chemical Engineering provides powerful modeling tools. Some innovations, especially in swallowing aids or nutrient delivery tools, connect to Food and Beverage Engineering.
Smaller, smarter rehabilitation devices are made possible through Nanotechnology in Chemical Engineering. Polymers and elastomers used in braces and flexible supports draw from Polymer and Plastics Engineering. Facility design for rehabilitation centers is informed by Civil Engineering, and project delivery may engage principles from Construction Management.
To safeguard continuity of care during emergencies—such as earthquakes or pandemics—principles from Earthquake and Disaster Engineering are applied to ensure facility resilience and equipment mobility. In sum, Rehabilitation Engineering embodies a transformative convergence of disciplines, uniting physical technology with human-centered design to empower recovery and restore independence.
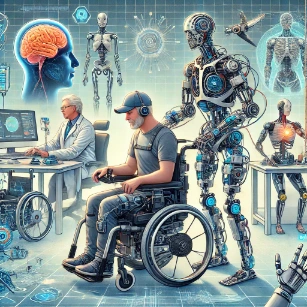
Convergence of human-robot physical interaction, virtual reality biofeedback, and closed-loop biosignal decoding in a clinical rehabilitation gymnasium.
This illustration presents rehabilitative engineering as a collaboration between people, clinicians, and advanced technology. At the center, a wheelchair user wears a VR headset, suggesting therapy that trains balance, movement, or coordination through immersive exercises. A humanoid assistive robot stands nearby, representing robotic support systems such as exoskeletons, powered braces, or intelligent mobility aids that help with gait training and daily tasks. Around them, medical staff monitor data on screens, highlighting how rehabilitation devices are guided by measurement, feedback, and personalization. In the background, prosthetic and skeletal visuals hint at biomechanical modeling and customized limb-support solutions. Overall, the image communicates the field’s goal: using engineering to reduce barriers, improve recovery outcomes, and help individuals regain confidence and independence in everyday life.
Biomedical Engineering – Knowledge Map
Rehabilitation Engineering (Current Page)
Focuses on restoring functional ability through technologies that assist movement, enhance independence, and adapt to user needs within the broader engineering framework.
Biomaterials
Provides the physical foundation for bio-compliant prosthetics, custom sockets, and wearable supports that remain durable under repeated mechanical stress.
Neural Engineering
Re-establishes direct communication between central neural pathways and robotic limbs to bypass spinal injuries and recover lost motor control.
Biomechanics
Evaluates kinetic force distribution, joint torques, and gait dynamics to optimize orthotic alignment and ergonomic efficiency.
Biomedical Signal Processing
Decodes surface electromyography (sEMG) and kinematic telemetry to drive intuitive, adaptive control loops in smart exoskeletons.
Medical Imaging
Tracks structural skeletal healing, muscle atrophy, and tissue regeneration over time to evaluate physical therapy progression.
Pharmaceutical Engineering
Supports therapy through localized anti-spasticity medications, analgesics, and targeted delivery formulations that reduce post-injury pain.
Tissue Engineering & Regenerative Medicine
Enhances physical rehabilitation by rebuilding damaged musculoskeletal tissue and peripheral nerve networks using bioactive scaffolds.
Cardiovascular Engineering
Monitors hemodynamic strain and cardiorespiratory load during robotic-assisted gait training in stroke or trauma survivors.
Bioinformatics
Analyzes patient phenotypic variations and motor learning datasets to personalize adaptive neuro-rehabilitation protocols.
Clinical Engineering
Oversees safety, calibration, and hospital fleet integration for motorized gait trainers, standing frames, and clinical telemetry systems.
Biomedical Engineering – Overview
Unites assistive technology, biological signal telemetry, and physical restoration under a unified healthcare engineering banner.
Major Areas of Rehabilitation Engineering
Mobility Aids
- Definition: Devices designed to enhance or restore mobility for people with physical impairments.
- Examples:
- Manual Wheelchairs: Adjustable seating systems, lightweight materials, customizable dimensions to fit user anatomy. Enhancements include off-road wheels and ergonomic components for outdoor use.
- Powered Wheelchairs: Battery-operated chairs featuring joystick controls, adjustable suspension, and IoT capabilities for remote health monitoring.
- Prosthetics: Artificial limbs built with carbon fiber, lightweight alloys, and advanced sockets—incorporating myoelectric or bionic control for natural movements.
- Orthotics: External support devices like AFOs (Ankle-Foot Orthoses) and KAFOs (Knee-Ankle-Foot Orthoses) designed to correct gait issues and improve posture.
- Walkers and Canes: Sleek, adjustable support aids with foldable frames and fall prevention sensors.
Powered Exoskeletons
- Definition: Wearable robotic frameworks enabling users with paralysis or muscle weakness to stand, walk, or lift loads.
- Applications:
- Rehabilitation for spinal cord injury, enabling gait training through repetitive movement.
- Neurological recovery after stroke via assisted ambulation.
- Industrial support for heavy lifting or repetitive tasks.
- Key Features:
- Embedded sensors (IMUs, pressure pads) and actuators driving movement based on user intent.
- Adjustable frames tailored to individual body shapes and functional needs.
- Energy-efficient power systems with rechargeable batteries offering several hours of use.
- Advanced control schemes such as adaptive gait, obstacle negotiation, and voice commands.
Prosthetics and Orthotic Devices
- Prosthetics:
- Robotic limbs featuring bionic joints, embedded EMG sensors, and AI-driven gait patterns.
- Materials like titanium, aluminum alloys, and carbon fiber for optimal weight-to-strength ratios.
- Orthotics:
- Custom-molded braces—with 3D-printed support structures—for spinal deformities and limb alignment.
- Functional braces designed to assist movement, reduce fatigue, and stabilize muscles or joints.
Assistive Robotics
- Definition: Robotic devices assisting with daily activities or therapeutic interventions.
- Examples:
- Robotic arms and manipulators helping wheelchair users with eating, drinking, or tool use.
- Companion robots providing reminders, social interaction, or fall detection assistance.
- Therapy robots offering precise repetitive motions for stroke, CP, or injury rehabilitation.
Communication Aids (Augmentative & Alternative Communication - AAC)
- Definition: Tools enabling communication for those with speech or language impairments.
- Examples:
- Speech-generating devices—ranging from text-to-speech tablet apps to dedicated voice output machines.
- Eye-tracking systems translating gaze direction into words or commands.
- Brain-computer interface systems converting neural signals into speech or typing actions.
Environmental Control Systems
- Definition: Smart systems that allow users to interact with their environments independently.
- Examples:
- Voice-activated home automation for controlling lighting, AC, doors, and appliances.
- Switch interfaces or gesture-based controls for household device access.
Virtual Reality (VR) & Augmented Reality (AR) in Rehabilitation
- Definition: Technology-driven environments facilitating physical and cognitive rehab.
- Applications:
- VR simulation platforms designed for speed, balance, coordination, and navigation training post-stroke.
- AR gamified solutions boosting motor function via interactive therapy routines.
- Features:
- Real-time performance metrics and customizable therapy intensity.
- Immersive visuals to motivate and track progress remotely.
Smart Wearables
- Definition: Sensor-equipped garments and devices that monitor activity and health.
- Examples:
- Inertial-sensor insoles that analyze gait, pressure distribution, and foot alignment.
- Wearable IMU-based bands measuring movements during rehab exercises.
- Health-monitoring wristbands tracking vitals like heart rate and temperature.
Emerging Subfields & Innovations
- Brain-Controlled Prosthetic Systems: BCI-enabled prosthetics allow movement via neural commands, accelerating response and adaptation.
- Exoskeletons with AI-Guided Learning: Adaptive machine learning algorithms personalize gait and posture assistance in real time.
- Tele-Rehabilitation Platforms: Remote therapy software linking therapists with patients through VR, wearables, and live feedback.
- 3D-Printed Assistive Devices: Personalized orthoses and prostheses produced with 3D printing for custom anatomical fit.
Key Considerations in Rehabilitation Engineering
- Person-Centered Design: Tailoring devices to physiological, emotional, and lifestyle needs.
- Usability & Training: Ensuring ease of use; supporting with training and follow-up adaptations.
- Interdisciplinary Collaboration: Combining clinical care, ergonomics, robotics, and software for cohesive solutions.
- Regulatory Compliance: Devices must meet medical device standards and gain approvals.
- Cost & Availability: Balancing innovation with affordability and access in healthcare systems.
Technologies in Rehabilitation Engineering
Robotics and Mechatronics
- Role: Combines robotics, sensors, actuators, and control systems to create intelligent devices that assist movement and rehabilitation.
- Key Technologies:
- High-precision motors and torque sensors to provide smooth, adaptive assistance based on user movement and force feedback.
- Embedded microcontrollers and real-time operating systems enabling precise control loops and safety monitoring.
- Haptic feedback elements that introduce tactile cues, enabling users to perceive pressure, grip, and positional information during therapy.
- Lightweight, exoskeletal frames using carbon-fiber composites and aluminum alloys for enhanced wearability and user comfort.
- Applications:
- Robotic exoskeletons: Assist walking, standing, and limb movement for people with spinal cord injuries, stroke, or neuromuscular disorders.
- Robotic gait training devices: Treadmill systems with harnesses and robotic arms that guide leg movements during rehabilitation exercises.
- Upper-limb rehab robots: Robots providing repetitive therapy exercises to restore arm and hand function post-stroke or injury.
Artificial Intelligence (AI) and Machine Learning
- Role: Empowers assistive technologies to analyze user behavior, adapt in real-time, and personalize therapy sessions.
- Techniques:
- Machine learning algorithms (SVMs, neural networks) trained on movement data to predict user intent and optimize assistance.
- Reinforcement learning systems that self-adjust device parameters to maximize therapeutic benefit over time.
- Real-time anomaly detection to spot signs of fatigue, misuse, or errors during sessions.
- Predictive analytics to identify risks of falls or health events based on movement patterns and physiological signals.
- Applications:
- Predictive therapy plans: AI analyzes historical session data to recommend optimal exercise routines and intensity levels.
- Adaptive prosthetics: Devices that learn amputee’s gait cycle, grip patterns, or joint movements and adjust control strategies dynamically.
- Smart exoskeletons: AI-managed assistance that adapts torque and timing to user’s strength and fatigue levels.
3D Printing and Additive Manufacturing
- Role: Enables rapid production of bespoke assistive devices—prosthetics, braces, and orthoses—at lower cost and fast turnaround.
- Technologies:
- FDM (Fused Deposition Modeling) for durable, lightweight prosthetic shells using PLA, ABS, or PETG.
- SLS (Selective Laser Sintering) and SLA (Stereolithography) for high-precision, biocompatible components, e.g., socket liners or joint parts.
- Multi-material printing to combine elastic, rigid, and flexible elements in a single device—mimicking natural limb properties.
- Custom-fit modeling using scans or CT data to create prosthetics and orthotics adapted to user’s anatomy.
- Applications:
- 3D-printed prosthetic limbs: User-tailored sockets, modular joints, and cosmetic covers at a fraction of traditional cost.
- Custom orthotic devices: Knee braces, wrist supports, and posture correctors made to match individual anthropometrics.
- Assistive tool grips: Personalized handles for utensils, pens, or kitchen tools to enhance independence.
Brain‑Computer Interfaces (BCIs)
- Role: Bridges the brain and external devices by decoding neural signals and translating them into control commands.
- Signal Acquisition:
- EEG headsets for non‑invasive detection of cortical activity.
- Implanted ECoG electrodes for high‑resolution brain signal capture.
- Intracortical microelectrodes for direct neuron-level measurement in experimental clinical therapies.
- Applications:
- Mind-controlled prosthetics: Patients operate robotic arms or hands via thought, supported by real-time neural decoding.
- Communication tools: BCIs enabling individuals with locked-in syndrome to type, select, or speak through neural interfaces.
- Neurofeedback systems: Users train brain patterns to control posture, balance, or speech output.
Internet of Things (IoT)
- Role: Connects devices, monitoring systems, and health data streams to create a smart rehabilitative ecosystem.
- Technologies:
- Low‑power wireless modules (Bluetooth LE, Zigbee) integrated in devices for seamless data transmission.
- Cloud-based platforms that aggregate data from wearables, home sensors, and clinical devices for remote analysis.
- Security frameworks ensuring encryption, data integrity, and HIPAA compliance when sharing health information.
- Edge-computing capabilities to process user data locally—providing instant feedback without reliance on internet connectivity.
- Applications:
- Smart home systems: Control lighting, HVAC, locks, and appliances using assistive control panels or voice commands.
- Remote health monitoring: Rehab professionals track vitals, movement, and compliance through wearable sensors.
- Fall detection and alert systems: Devices that detect falls or irregular gait and automatically notify caregivers.
Cross‑Technology Synergies
- Combining AI with IoT enables adaptive exoskeletons to auto-tune support levels based on live gait and fatigue data.
- Using robotics, BCIs, and 3D printing together to create fully personalized, neural-controlled prosthetics.
- Remote rehabilitation setups using VR interfaces, wearable sensors, and teletherapy for home-based recovery.
Applications and Benefits of Rehabilitative Engineering
Restoration of Mobility
- Rehabilitative engineering enables individuals with limb loss, paralysis, or neuromuscular disorders to regain functional movement through assistive technologies.
- Powered Exoskeletons: Wearable robotic suits assist walking for individuals with spinal cord injuries or stroke, improving muscle strength, circulation, and balance.
- Advanced Prosthetics: Myoelectric and bionic limbs replicate natural movements using sensors and motors, providing users with greater control, dexterity, and comfort.
- Mobility Robots: Autonomous wheelchairs and stair-climbing devices allow users to navigate indoor and outdoor environments more safely and efficiently.
Enhanced Independence
- Technologies that allow users to interact with and control their environment without reliance on caregivers are central to rehabilitative engineering.
- Environmental Control Systems: Devices such as voice-activated appliances, smart lighting, and adaptive interfaces empower users to operate daily utilities independently.
- IoT-Connected Devices: Smart homes integrated with rehabilitation tools provide seamless access to healthcare, security, and comfort for users with limited mobility.
- Hands-Free Interfaces: Eye-tracking or sip-and-puff systems enable control over computers, phones, and televisions, reducing dependency and improving autonomy.
Improved Communication
- For individuals with speech or motor impairments, augmentative and alternative communication (AAC) systems transform lives by enabling expression and interaction.
- Speech-Generating Devices (SGDs): Use synthesized or recorded speech to vocalize typed or selected phrases, supporting users with conditions such as ALS, cerebral palsy, or aphasia.
- Eye-Tracking Communication Systems: Allow users to navigate on-screen keyboards or select icons using gaze direction, useful for individuals with locked-in syndrome or severe mobility limitations.
- Brain-Computer Interfaces (BCIs): Translate neural activity into digital commands, allowing users to type or speak virtually using only their thoughts.
Accelerated Rehabilitation
- By integrating robotics, feedback systems, and adaptive algorithms, rehabilitative engineering significantly enhances the effectiveness and efficiency of therapeutic interventions.
- Robotic Therapy Devices: Exoskeletal arms and legs guide patients through repetitive movement patterns, which are critical for neuroplasticity and functional recovery.
- Virtual Reality (VR) Therapy: Immersive environments encourage participation in engaging and measurable therapy sessions, improving motivation and outcomes.
- Sensor-Based Monitoring: Wearables and smart insoles track range of motion, balance, and gait, offering clinicians objective data to tailor therapy plans.
Increased Quality of Life
- Rehabilitative engineering improves not only physical capability but also mental health, emotional well-being, and social integration.
- Customized Solutions: 3D-printed prosthetics, modular exoskeletons, and ergonomic assistive devices are tailored to individual user needs, ensuring comfort and effectiveness.
- Psychosocial Benefits: Gaining independence, mobility, and communication capacity helps users reintegrate into family, community, and work life with greater confidence and dignity.
- Reduced Caregiver Burden: Technologies that support user autonomy reduce strain on family members and healthcare providers, promoting more sustainable long-term care arrangements.
Broader Societal Impact
- Accessibility Innovation: Technologies initially developed for rehabilitation are influencing broader accessibility improvements in workplaces, education, and transportation systems.
- Cost-Effective Healthcare: By enabling home-based care and reducing hospital visits, rehabilitative technologies contribute to more efficient healthcare delivery and cost savings.
- Inclusive Product Design: Advances in inclusive design foster social equity by ensuring that products, services, and environments are usable by the widest possible range of people.
Challenges and Future Outlook in Rehabilitation Engineering
1. Cost and Accessibility
- High development and production costs often restrict widespread availability of advanced assistive technologies, leaving many users unable to afford essential rehabilitation equipment.
- Developing countries and underserved communities are particularly impacted by high prices, exacerbating healthcare disparities.
- Efforts to lower costs through innovative production methods, such as additive manufacturing (3D printing), are promising but still face significant scalability and regulatory hurdles.
2. Customization and Adaptability
- Creating personalized rehabilitation devices tailored to individual needs requires extensive time, resources, and specialized expertise.
- Users differ greatly in their physiological requirements, making standardization difficult and necessitating a highly individualized design approach.
- Adaptable and modular device designs that can evolve alongside a user's changing physical conditions present promising yet challenging solutions.
3. Durability and Maintenance
- Assistive devices must withstand rigorous daily use, frequent handling, and exposure to varying environmental conditions, all of which present substantial durability challenges.
- Mechanical components, sensors, batteries, and electronics in devices such as powered wheelchairs and exoskeletons are prone to wear and failure, requiring robust designs and regular maintenance.
4. User Training and Acceptance
- Even the most advanced assistive technologies may fail to improve quality of life if users lack proper training and support to fully utilize them.
- Acceptance and consistent use of rehabilitation devices often depend on the user’s psychological comfort, perceived benefit, and ease of integration into social and daily activities.
5. Regulatory and Safety Standards
- Rehabilitation engineering devices must meet strict regulatory requirements to ensure user safety, reliability, and therapeutic effectiveness.
- Compliance with standards from agencies such as the U.S. Food and Drug Administration (FDA) and European Medicines Agency (EMA) demands extensive documentation, testing, and validation procedures.
6. Technological Integration and Compatibility
- Integrating diverse assistive devices with existing healthcare infrastructure and home automation systems presents significant technical and logistical challenges.
- Ensuring seamless interoperability between rehabilitation devices and digital health ecosystems requires standardized communication protocols and compatible data formats.
7. Ethical and Privacy Considerations
- The proliferation of sophisticated rehabilitation technologies raises ethical questions regarding consent, autonomy, and user rights.
- Data collected from assistive technologies can be highly sensitive, necessitating stringent data management, protection, and privacy practices to maintain user confidentiality.
Contemporary 2026 AI-Era Computational Paradigms in Rehabilitation Robotics
Modern neuro-rehabilitation and motorized assistive hardware rely on real-time adaptive computation that bridges human neural intent with physical machine kinematics:
- Physics-Informed Neural Networks (PINNs) for Musculoskeletal Dynamics: PINNs estimate in vivo tendon forces, joint contact pressures, and muscle activations by enforcing Hill-type muscle contraction mechanics and Euler-Lagrange multibody dynamics directly within the neural loss function: $$\mathcal{L}_{\text{PINN}} = \left\| \mathbf{M}(\mathbf{q})\ddot{\mathbf{q}} + \mathbf{C}(\mathbf{q},\dot{\mathbf{q}})\dot{\mathbf{q}} + \mathbf{G}(\mathbf{q}) - \mathbf{\tau}_{\text{exo}} - \mathbf{J}_{\text{mus}}^T \mathbf{F}_{\text{mus}} \right\|^2 + \lambda \sum_m \left\| \dot{F}_{\text{mus},m} - \psi(a_m, l_m, v_m) \right\|^2$$ where \(\mathbf{M}(\mathbf{q})\) is the anatomical inertia matrix, \(\mathbf{C}\) contains Coriolis terms, \(\mathbf{G}\) is gravity, and \(\mathbf{F}_{\text{mus}}\) represents internal muscle force vectors. This enables real-time joint torque estimation without requiring invasive bone pins or fluoroscopic motion tracking.
- Invariant Extended Kalman Filtering (IEKF) for Lie Group Kinematics: In contrast to standard Kalman filters that accumulate orientation errors during rapid limb movement or magnetic disturbances, IEKF operates directly on the matrix Lie group \(\text{SE}(3)\). By preserving geometric invariants during sensor fusion between IMUs, joint encoders, and ground reaction plates, the system achieves sub-degree pelvic tilt and knee angle tracking accuracy during irregular pathological ambulation.
- Deep Reinforcement Learning & Zero-Impedance Control: Real-time Actor-Critic architectures infer user movement intent from surface electromyography (sEMG) arrays within \(10\,\text{ms}\), dynamically modulating admittance gains (\(M_d, B_d, K_d\)) to ensure the exoskeleton remains transparent when the patient moves voluntarily and applies corrective torque only upon detecting gait freezing or kinematic deviations.
Systems Engineering Trade-Off Analysis in Assistive Technology
Engineering assistive and rehabilitative devices requires balancing biomechanical support, ergonomic comfort, electrical efficiency, and safety. The following structured matrix outlines core design compromises:
| Design Domain | Parameter Dimension A | Parameter Dimension B | Critical Multi-Variable Compromise |
|---|---|---|---|
| Exoskeleton Actuation | High Peak Torque Output (\(\tau_{\max} \gt 80\,\text{Nm}\) for sit-to-stand) | Actuator Mass & Reflected Inertia (\(m_{\text{joint}} \lt 1.5\,\text{kg}\)) | High gear-ratio cycloidal drives provide necessary assistance torques but introduce high mechanical impedance, causing resistance to voluntary user movement and increasing metabolic transport cost. |
| Prosthetic Socket Interface | Rigid Mechanical Load Transfer (High Carbon Laminate Modulus) | Interfacial Tissue Compliance & Capillary Perfusion (\(P \lt 32\,\text{mmHg}\)) | Maximizing structural stability during heel strike and push-off versus preventing localized shear stress, deep tissue injury, and ischemic necrosis over bony residual limb prominences. |
| AAC Sensor Modality | Fast Character Entry Rate (High-Resolution Invasive Intracortical BCI) | Long-Term Clinical Safety (Non-Invasive Video Eye-Tracking / EEG) | High-bandwidth communication (\(\gt 60\,\text{words/min}\)) requiring neurosurgical craniotomy and bearing infection/gliosis risks versus non-invasive gaze tracking (\(\sim 15\text{--}25\,\text{words/min}\)) prone to lighting variations and user eyelid fatigue. |
| Functional Electrical Stimulation (FES) | Recruitment of Deep Motor Units (High Pulse Width & Current: \(I \gt 80\,\text{mA}\)) | Nociceptive Pain Threshold & Rapid Muscle Fatigue Minimization | Achieving sufficient tetanic muscle force for functional foot clearance during swing phase versus causing sensory discomfort and accelerating neuromuscular junction neurotransmitter depletion. |
Interactive Robotic Exoskeleton Torque & Gait Assist Simulator
Adjust user muscle weakness level, robotic motor torque assistance (Nm), and gait cadence to simulate joint angle trajectory compensation during clinical gait rehabilitation.
Mathematical model: Dynamic knee flexion angle \(\theta_{\text{knee}}(t)\) modulated by motor assistance and cadence shift. Interactive module: https://prep4uni.online/stem/physical-technologies/biomedical-engineering/rehabilitation-engineering/
Why Study Rehabilitation Engineering
Improving Quality of Life
Customizing Solutions for Individual Needs
Integration with Clinical Practice
Use of Sensors and Control Systems
Applications in Aging and Recovery
Rehabilitation Engineering: Conclusion
Rehabilitation engineering is revolutionizing the way individuals with disabilities interact with the world, empowering them with innovative devices and technologies that restore independence and improve quality of life. From assistive robotics and advanced prosthetics to brain-computer interfaces and smart environments, this field is continuously evolving to address the diverse needs of patients. As technology advances, rehabilitation engineering will continue to deliver more personalized, accessible, and effective solutions, breaking down barriers and enabling people with disabilities to lead fuller, more autonomous lives.
Frequently Asked Questions on Rehabilitation Engineering
Is rehabilitation engineering the same as physiotherapy?
No. Physiotherapists deliver hands-on assessment and treatment, such as exercises and manual therapy. Rehabilitation engineers design and adapt technologies—like wheelchairs, exoskeletons or communication devices—that therapists and patients then use in rehabilitation programmes. The fields are complementary and often work closely together.
Do rehabilitation engineers work directly with patients?
In many settings they do. Rehabilitation engineers may attend clinics, observe therapy sessions and carry out assessments to understand a person’s environment and functional goals. This direct contact helps them customise devices and adjust designs based on real feedback from users and clinicians.
What is the difference between assistive technology and rehabilitation technology?
Assistive technology is any device or system that helps a person perform everyday tasks more independently over the long term, such as a powered wheelchair or speech-generating device. Rehabilitation technology is often used in therapy to restore or improve function, such as robotic gait trainers or upper-limb exercise devices. In practice, many systems play both roles depending on how they are used.
Are high-tech robotic devices always better than low-tech solutions?
Not necessarily. High-tech systems can offer powerful features, but they may be expensive, complex to maintain or difficult to use in some settings. Sometimes a simple, low-tech solution—such as a customised seating system or adapted handle—can be more reliable, affordable and acceptable to the user. Good rehabilitation engineering chooses the simplest design that meets the person’s goals.
What career paths are available in rehabilitation engineering?
Graduates can work in hospitals and rehabilitation centres, assistive technology service providers, device manufacturers, research institutes, start-ups developing wearable or robotic systems, and government or non-profit organisations focused on disability services and standards. Many roles mix technical design with clinical teamwork and user support.
How is data from smart rehabilitation devices used?
Data from sensors in exoskeletons, therapy robots or wearable devices can track movement, exercise intensity and adherence over time. Clinicians use this information to adjust treatment plans, while engineers use it to improve device algorithms and interfaces. At the same time, data must be handled carefully to protect privacy and comply with health data regulations.
End-of-Page Practice & Assessment Module
Section 1: Foundational Review Questions
Testing core principles, assistive technology classifications, and user-centered clinical workflows. Toggle each box to reveal the answer.- What is rehabilitation engineering, and how does it differ from traditional clinical therapy?
Click to Toggle Answer
Answer: Rehabilitation engineering applies engineering principles to design, test, and adapt assistive devices and robotic systems that restore or enhance physical and cognitive function. Unlike physical therapy, which focuses on manual treatment and exercise regimes, rehabilitation engineering develops the underlying technological hardware and software tools used by clinicians and patients.
- What are the primary differences between assistive technology and rehabilitation technology?
Click to Toggle Answer
Answer: Assistive technology refers to long-term devices (such as powered wheelchairs, speech-generating devices, or AAC aids) used by individuals to maintain daily independence. Rehabilitation technology encompasses therapeutic equipment (such as robotic gait trainers or EMG-driven exoskeletons) used temporarily in clinical settings to promote neuroplasticity and functional recovery.
- How do myoelectric sensors operate in modern upper-limb prosthetic devices?
Click to Toggle Answer
Answer: Surface EMG electrodes embedded inside the prosthetic socket detect microvolt-level electrical signals generated during residual muscle contraction. Onboard microcontrollers filter and amplify these signals, translating user muscle intent into motorized hand grasp or wrist rotation movements.
- What role does person-centered design play in reducing device abandonment?
Click to Toggle Answer
Answer: Person-centered design actively incorporates the user's specific physiological measurements, home environment constraints, cognitive comfort, and lifestyle preferences early in the development cycle. This ensures the final solution is intuitive, durable, and practical, directly preventing technology rejection.
- How do Ankle-Foot Orthoses (AFOs) assist patients with drop-foot gait pathology?
Click to Toggle Answer
Answer: An AFO provides rigid or dynamic carbon-fiber structural support holding the ankle joint in a neutral (90-degree) dorsiflexed position during the swing phase of gait, preventing toe drag and facilitating smooth heel-strike transitions.
- What are the core components of an Augmentative and Alternative Communication (AAC) system?
Click to Toggle Answer
Answer: Input interfaces (eye-tracking cameras, sip-and-puff switches, or touchscreens), a symbol selection/language processing engine, and an output display or text-to-speech synthesizer that vocalizes user selections.
- Why are lower-limb powered exoskeletons effective in neuro-rehabilitation following spinal cord injury?
Click to Toggle Answer
Answer: They provide motorized, highly repeatable gait-cycle joint assistance that stimulates afferent proprioceptive feedback to the spinal cord and brain, promoting neuroplastic rewiring and improving cardiovascular health.
- How do wearable Inertial Measurement Units (IMUs) support gait assessment outside the laboratory?
Click to Toggle Answer
Answer: IMUs combine 3-axis accelerometers, gyroscopes, and magnetometers to track joint angles, stride symmetry, and cadence continuously during real-world patient activity without requiring optical motion-capture camera setups.
Section 2: Thought-Provoking & Scenario-Based Questions
Evaluating clinical trade-offs, advanced material selection, and ethical BCI integration scenarios. Toggle each box to reveal the answer.- When designing a wheelchair seating system, how do engineers balance pressure ulcer prevention with postural stability?
Click to Toggle Answer
Answer: Engineers utilize multi-layered contoured seating architectures combining high-density supportive polyurethane foam bases with fluid or air-cell overlays (e.g., ROHO technology) over the ischial tuberosities. This redistributes peak interfacial pressures below \(32\,\text{mmHg}\) (capillary closing pressure) while maintaining lateral pelvic stability for active propulsion.
- What trade-offs exist between non-invasive EEG-based BCIs and invasive microelectrode arrays for communication in locked-in syndrome?
Click to Toggle Answer
Answer: EEG BCIs are non-surgical, low-cost, and safe, but offer limited signal bandwidth, high noise sensitivity, and slow typing rates (\(\sim 5\text{--}10\,\text{words/min}\)). Invasive microelectrode arrays provide high-resolution single-unit neural recordings enabling fast, fluent text generation (\(\gt 60\,\text{words/min}\)), but carry neurosurgical risks, infection possibilities, and potential tissue scarring over time.
- How can machine learning reinforcement algorithms optimize active knee joint resistance during staircase descent?
Click to Toggle Answer
Answer: By processing real-time IMU inclination angles and socket load-cell data, reinforcement learning models dynamically adjust hydraulic or magnetorheological damper valves in the prosthetic knee. This provides smooth, eccentric damping tailored to user weight and stair pitch without requiring manual mode switching.
- Why is closed-loop functional electrical stimulation (FES) superior to open-loop FES for restoring hand grasp in stroke survivors?
Click to Toggle Answer
Answer: Closed-loop FES measures real-time force sensor feedback from the fingertips and adjusts electrical pulse pulse-width or frequency dynamically. This prevents muscle fatigue and slip, whereas open-loop FES applies constant pulse trains regardless of object weight or muscle exhaustion.
- What biomechanical factors make carbon-fiber energy-storage-and-return (ESR) prosthetic feet advantageous for active amputees?
Click to Toggle Answer
Answer: ESR carbon-fiber spring heels deflect during heel strike to absorb impact kinetic energy, storing it elastically and releasing it as forward propulsion torque during late-stance toe-off, mimicking intact gastrocnemius muscle function.
- How do virtual reality (VR) biofeedback platforms accelerate upper-limb motor rehabilitation post-stroke?
Click to Toggle Answer
Answer: VR provides engaging visual and auditory feedback that enhances reward-based motor learning. By manipulating virtual object weights and task goals, VR triggers mirror neuron activation, encouraging higher repetition counts and driving neuroplastic cortical reorganization.
- What regulatory challenges exist when approving AI-driven adaptive prosthetics that self-calibrate over time?
Click to Toggle Answer
Answer: Traditional regulatory frameworks (FDA 510(k)) require fixed algorithm locks. Self-learning adaptive AI systems continuously modify control weights post-market, requiring novel "Predetermined Change Control Plans" (PCCPs) to ensure algorithm updates remain within safe operational bounds without unreviewed drift.
Section 3: Numerical Problems & Step-by-Step Solutions
Quantitative analysis of biomechanical force distribution, wheelchair ramp slope mechanics, battery power management, and FES pulse parameters. Toggle each box to reveal the full calculation.- Problem 1: Wheelchair Ramp Slope Mechanics & Propulsion Force
A manual wheelchair user with total combined mass \(m = 85\,\text{kg}\) (user plus wheelchair) navigates up a standard ADA-compliant ramp with a slope angle \(\theta = 4.76^\circ\) (1:12 rise-to-run ratio). Assuming rolling resistance coefficient \(\mu_r = 0.03\) and gravitational acceleration \(g = 9.81\,\text{m/s}^2\), calculate the minimum steady propulsion force \(F_{\text{prop}}\) in Newtons required to maintain constant speed.Click to Toggle Step-by-Step Solution
Step 1: Formulate the force balance along the incline
$$F_{\text{prop}} = F_{\text{gravity, parallel}} + F_{\text{rolling friction}}$$ $$F_{\text{prop}} = m g \sin(\theta) + \mu_r m g \cos(\theta)$$ Step 2: Calculate gravitational weight vector \(W\)
$$W = m g = 85\,\text{kg} \times 9.81\,\text{m/s}^2 = 833.85\,\text{N}$$ Step 3: Compute parallel gravity component
$$\sin(4.76^\circ) \approx 0.08294$$ $$F_{\text{gravity, parallel}} = 833.85\,\text{N} \times 0.08294 = 69.16\,\text{N}$$ Step 4: Compute rolling friction component
$$\cos(4.76^\circ) \approx 0.99656$$ $$F_{\text{rolling friction}} = 0.03 \times 833.85\,\text{N} \times 0.99656 = 24.93\,\text{N}$$ Step 5: Calculate total propulsion force
$$F_{\text{prop}} = 69.16\,\text{N} + 24.93\,\text{N} = \mathbf{94.09\,\text{N}}$$ - Problem 2: Powered Exoskeleton Actuator Torque Requirement
During standing balance recovery, a lower-limb exoskeleton must generate an extension torque at the knee joint to support an upper-body segment mass \(m = 55\,\text{kg}\) centered at distance \(r = 0.42\,\text{m}\) horizontally from the knee axis. Calculate the required knee motor torque \(M_{\text{knee}}\) in Newton-meters (\(\text{Nm}\)) assuming static equilibrium.Click to Toggle Step-by-Step Solution
Step 1: Formula for moment due to gravity
$$M_{\text{knee}} = F \times r = (m g) \times r$$ Step 2: Calculate downward gravitational force
$$F = 55\,\text{kg} \times 9.81\,\text{m/s}^2 = 539.55\,\text{N}$$ Step 3: Compute knee joint torque
$$M_{\text{knee}} = 539.55\,\text{N} \times 0.42\,\text{m} = \mathbf{226.61\,\text{Nm}}$$ - Problem 3: Powered Wheelchair Battery Capacity & Range Estimation
A powered wheelchair is driven by two \(24\,\text{V}\), \(250\,\text{W}\) DC motors operating at an average \(40\%\) load factor during outdoor travel. The wheelchair is powered by a \(24\,\text{V}\), \(50\,\text{Ah}\) lithium-ion battery pack. Assuming an \(85\%\) battery discharge efficiency limit to prevent cell degradation, calculate the continuous operating runtime in hours and total travel distance in kilometers at a constant speed \(v = 6.0\,\text{km/h}\).Click to Toggle Step-by-Step Solution
Step 1: Calculate total average power draw
$$\text{Total Rated Power} = 2 \times 250\,\text{W} = 500\,\text{W}$$ $$\text{Average Power Draw} = 500\,\text{W} \times 0.40 = 200\,\text{W}$$ Step 2: Calculate usable battery energy capacity in Watt-hours (\(\text{Wh}\))
$$\text{Nominal Energy} = 24\,\text{V} \times 50\,\text{Ah} = 1200\,\text{Wh}$$ $$\text{Usable Energy} = 1200\,\text{Wh} \times 0.85 = 1020\,\text{Wh}$$ Step 3: Compute runtime hours
$$\text{Runtime} = \frac{1020\,\text{Wh}}{200\,\text{W}} = \mathbf{5.10\,\text{Hours}}$$ Step 4: Compute total travel distance
$$\text{Distance} = 5.10\,\text{h} \times 6.0\,\text{km/h} = \mathbf{30.6\,\text{km}}$$ - Problem 4: Seating Pressure Distribution & Ischial Contact Area
A seated user weighs \(W = 700\,\text{N}\). Biomechanical force plate testing indicates that \(65\%\) of total body weight is supported directly through the ischial tuberosities on the wheelchair cushion. If the maximum safe skin interface capillary pressure limit is \(P_{\text{limit}} = 32\,\text{mmHg}\) (\(1\,\text{mmHg} = 133.322\,\text{Pa}\)), calculate the minimum contact area in \(\text{cm}^2\) required across the cushion to prevent tissue ischemia.Click to Toggle Step-by-Step Solution
Step 1: Calculate load borne by ischial contact area
$$F = 700\,\text{N} \times 0.65 = 455\,\text{N}$$ Step 2: Convert pressure threshold to Pascals (\(\text{N/m}^2\))
$$P_{\text{limit}} = 32\,\text{mmHg} \times 133.322\,\text{Pa/mmHg} = 4266.3\,\text{Pa}$$ Step 3: Calculate required minimum surface area in \(\text{m}^2\)
$$A = \frac{F}{P_{\text{limit}}} = \frac{455\,\text{N}}{4266.3\,\text{Pa}} = 0.10665\,\text{m}^2$$ Step 4: Convert \(\text{m}^2\) to \(\text{cm}^2\)
$$A = 0.10665 \times 10{,}000 = \mathbf{1066.5\,\text{cm}^2}$$ - Problem 5: Functional Electrical Stimulation (FES) Charge Delivery
An FES neuro-orthotic pulse generator delivers biphasic square-wave stimulation pulses to the quadriceps muscle. Each pulse phase has a current amplitude \(I = 45\,\text{mA}\) and a pulse width \(t = 300\,\mu\text{s}\). Calculate the electrical charge per pulse phase in microcoulombs (\(\mu\text{C}\)), and determine total energy delivered per pulse across a skin-electrode impedance \(R = 1.2\,\text{k}\Omega\).Click to Toggle Step-by-Step Solution
Step 1: Calculate charge per phase (\(Q\))
$$Q = I \times t = (45 \times 10^{-3}\,\text{A}) \times (300 \times 10^{-6}\,\text{s}) = 1.35 \times 10^{-5}\,\text{C} = \mathbf{13.5\,\mu\text{C}}$$ Step 2: Calculate Power during pulse phase
$$P = I^2 R = (0.045\,\text{A})^2 \times 1200\,\Omega = 0.002025 \times 1200 = 2.43\,\text{W}$$ Step 3: Calculate energy per pulse phase in Joules
$$E = P \times t = 2.43\,\text{W} \times 300 \times 10^{-6}\,\text{s} = 0.000729\,\text{J} = \mathbf{0.729\,\text{mJ}}$$ - Problem 6: Upper-Limb Prosthetic Elbow Gear Ratio Mechanics
A bionic arm elbow joint actuator utilizes a brushless DC motor running at \(N_{\text{motor}} = 3600\,\text{rpm}\) producing torque \(T_{\text{motor}} = 0.12\,\text{Nm}\). If a planetary gearbox with speed reduction ratio \(G = 120:1\) and mechanical efficiency \(\eta = 82\%\) is attached, calculate the output joint rotational speed in degrees per second (\(^\circ/\text{s}\)) and output joint torque \(T_{\text{joint}}\) in \(\text{Nm}\).Click to Toggle Step-by-Step Solution
Step 1: Calculate output rotational speed in RPM
$$N_{\text{joint}} = \frac{N_{\text{motor}}}{G} = \frac{3600\,\text{rpm}}{120} = 30\,\text{rpm}$$ Step 2: Convert RPM to degrees per second
$$\text{Speed} = \frac{30\,\text{rev}}{\text{min}} \times \frac{360^\circ}{\text{rev}} \times \frac{1\,\text{min}}{60\,\text{s}} = \mathbf{180^\circ/\text{s}}$$ Step 3: Calculate output joint torque with efficiency
$$T_{\text{joint}} = T_{\text{motor}} \times G \times \eta$$ $$T_{\text{joint}} = 0.12\,\text{Nm} \times 120 \times 0.82 = \mathbf{11.81\,\text{Nm}}$$ - Problem 7: Eye-Tracking AAC System Processing Throughput
An AAC gaze-tracking camera samples eye position at \(120\,\text{frames per second (fps)}\). Each uncompressed video frame has a resolution of \(640 \times 480\,\text{pixels}\) with \(8\text{-bit}\) grayscale depth. Calculate the raw video data stream throughput generated prior to feature extraction in Megabytes per second (\(\text{MB/s}\)).Click to Toggle Step-by-Step Solution
Step 1: Calculate bytes per single image frame
$$\text{Bytes/frame} = 640 \times 480\,\text{pixels} \times 1\,\text{byte/pixel} = 307{,}200\,\text{Bytes}$$ Step 2: Compute total data throughput per second
$$\text{Data Rate} = 307{,}200\,\text{Bytes/frame} \times 120\,\text{frames/sec} = 36{,}864{,}000\,\text{Bytes/sec}$$ Step 3: Convert to MB/s (using decimal metric scale)
$$\text{Throughput} = \frac{36{,}864{,}000}{1{,}000{,}000} = \mathbf{36.86\,\text{MB/s}}$$