

IDEF0 functional decomposition of Cardiovascular Engineering Education: turning biomedical inputs into engineering competencies under scientific and regulatory controls, enabled by tools and practice.

Cardiovascular engineering blends medicine, mechanics, and smart technology to design safer, more precise heart-care solutions.
Biomedical Engineering – Knowledge Map & Cluster Navigation
Cardiovascular Engineering (Current Node)
Examines how blood circulation and cardiac activity are maintained, controlled, and influenced within the vascular network.
Medical Imaging
Captures dynamic flow and structural features of the heart and vessels for non-invasive visual assessment and anatomical modeling.
Biomedical Signal Processing
Interprets electrical (ECG) and pressure-based waveforms to characterize rhythm abnormalities and hemodynamics.
Neural Engineering
Influences circulatory function through autonomic neural pathways regulating heart rate variability and vascular tone.
Pharmaceutical Engineering
Develops targeted drug delivery systems that alter flow dynamics, regulate pressure, and deliver anti-thrombotic agents.
Rehabilitation Engineering
Monitors cardiovascular response during physical recovery to guide safe post-cardiac surgery therapy.
Clinical Engineering
Ensures hospital deployment, safety compliance, and maintenance of circulatory life-support equipment.
Biomechanics
Analyzes physical stress, wall shear strain, and fluid mechanics within arterial walls and cardiac chambers.
Biomaterials
Provides hemocompatible polymers, alloys, and tissue scaffolds capable of enduring continuous blood contact.
Tissue Engineering & Regenerative Medicine
Biofabricates autologous heart valves, vascular grafts, and cardiac patches to restore native tissue function.
Bioinformatics
Maps genetic markers and biomarker profiles to predict cardiovascular disease progression and tailor therapy.
Biomedical Engineering (Hub Overview)
Integrates all subdisciplines into a broader clinical framework for healthcare technological innovation.
Core Areas of Cardiovascular Engineering
Artificial Hearts and Ventricular Assist Devices (VADs)
- Artificial Hearts:
- Fully self-contained mechanical units mimicking the pumping action of a natural heart, with advanced sensors and feedback systems that adjust pumping speed in response to physical activity and physiological demands.
- Examples include the SynCardia Total Artificial Heart, used as a bridge-to-transplant device, and the Carmat bioprosthetic heart, which incorporates biological materials to reduce rejection risk.
- Artificial hearts are critical for patients whose cardiac function has irreparably failed and who are not candidates for donor heart transplantation.

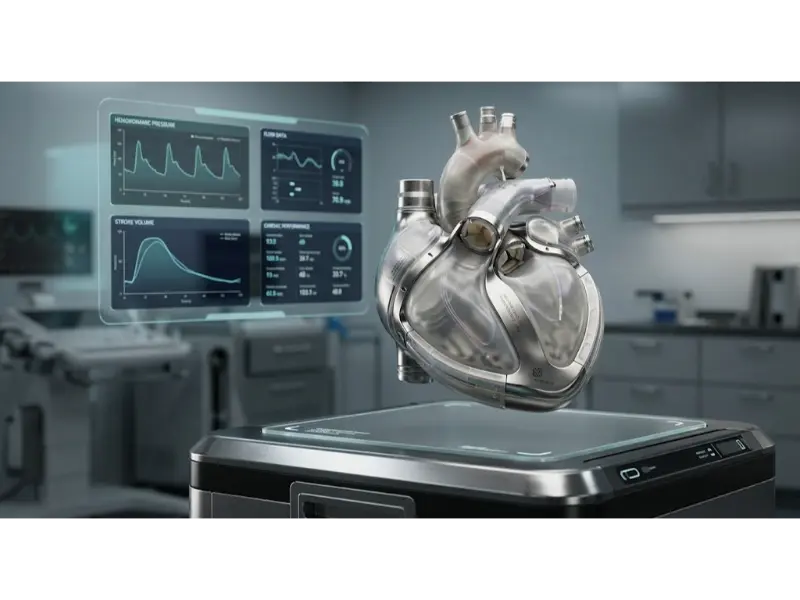
Total Artificial Heart (TAH) engineering: dual-chamber mechanical ventricle architecture integrating biocompatible titanium casings, bioprosthetic inflow/outflow valves, and embedded micro-sensors for real-time hemodynamic autoregulation.
- Ventricular Assist Devices (VADs):
- Engineered mechanical pumps attached to one or both ventricles to augment cardiac output and maintain systemic circulation.
- Left VADs (LVADs): Support the left ventricle, commonly used in patients with left-sided heart failure. Devices like the HeartMate 3 use magnetically levitated rotors to improve durability and reduce hemolysis.
- Right VADs (RVADs): Support the right ventricle, often deployed in cases of right ventricular failure post LVAD implantation or due to pulmonary hypertension.
- Biventricular VADs (BiVADs): Provide support for both ventricles in cases of global heart failure.
- Advancements include sensor-augmented states to prevent pump thrombosis and multi-year battery life to support ambulatory living.
Stents and Angioplasty Devices
- Stents:
- Mesh-like tubes implanted in stenotic (narrowed) arteries to scaffold the vessel open, ensuring adequate blood perfusion.
- Bare-Metal Stents (BMS): Simple metallic scaffolds; affordable and durable, but associated with higher rates of restenosis due to neointimal proliferation.
- Drug-Eluting Stents (DES): Coated with antiproliferative agents such as sirolimus or paclitaxel, reducing restenosis risk. Examples include the Xience and Endeavor line of stents.
- Bioabsorbable Stents: Comprised of biodegradable polymers like PLLA or magnesium alloys that gradually dissolve, leaving the artery with restored vessel flexibility.
- Angioplasty Balloons:
- Inflatable balloons that mechanically dilate vessels narrowed due to plaque build-up or thrombus.
- They precede stent deployment in Percutaneous Coronary Intervention (PCI) to prepare the vessel and reduce complications like dissection.
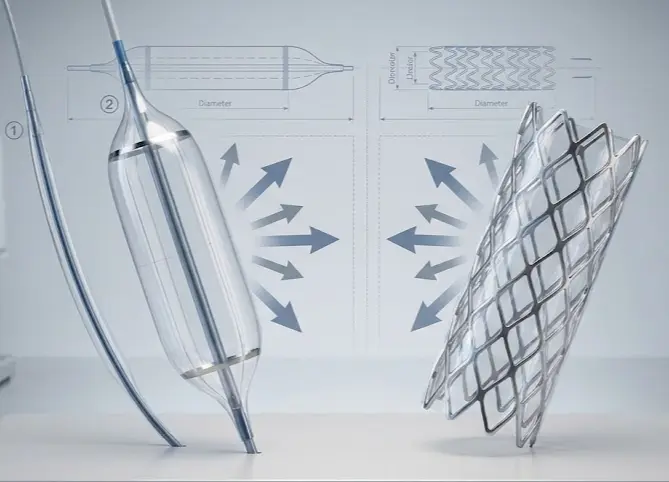
Comparative mechanics of angioplasty balloons and endovascular stents: the polymer balloon (left) delivers hydraulic radial expansion to dilate stenotic lesions, while the metallic mesh stent scaffold (right) provides permanent structural support to prevent elastic recoil.
Vascular Grafts and Bypass Devices
- Definition: Engineered conduits, either synthetic or biological, to restore circulation across blocked or compromised vessels.
- Applications:
- Coronary Artery Bypass Grafting (CABG): Grafts are used to bypass occluded coronary arteries using vessels such as the internal mammary artery or saphenous vein.
- Peripheral Artery Disease (PAD): Bypassing critical blockages in the limbs to prevent ischemia and lower-limb amputation.
- Materials Used:
- Synthetic Polymers: ePTFE and Dacron are widely used due to their mechanical strength and surgical compatibility.
- Biological Grafts: Autografts (from the patient) and allografts (from donors) are used where long-term patency and clot-resistance are vital.
Heart Valve Prostheses
- Mechanical Heart Valves:
- Constructed from durable materials such as pyrolytic carbon and titanium, these valves can last several decades.
- Require lifelong anticoagulation therapy to prevent thromboembolic events.
- Bioprosthetic Valves:
- Made from biological tissues—porcine, bovine pericardium, or human cadaveric tissue.
- Offer lower thrombosis risk and generally do not require long-term anticoagulation.
- Trade-off: limited lifespan (10–15 years) due to tissue degeneration.
- Transcatheter Aortic Valve Replacement (TAVR):
- Minimally invasive, percutaneous valve implantation, revolutionizing treatment for elderly, high-risk patients.
- Latest systems include Edwards Sapien and Medtronic CoreValve, with smaller delivery sheaths and improved sealing skirts.
Cardiovascular Tissue Engineering
- Definition: Combining cells, scaffolds, and bioactive molecules in physiologically relevant environments to promote tissue regeneration.
- Applications:
- Bioengineered heart valves grown from the patient’s own cells to reduce immune rejection.
- Tissue-engineered vascular grafts using biodegradable polymers seeded with endothelial and smooth muscle cells.
- Cardiac patches for post-myocardial infarction repair, enabling electrical coupling and mechanical integration with native myocardium.
Cardiovascular Diagnostics and Imaging
- Imaging Technologies:
- Echocardiography: Non-invasive ultrasound imaging for assessing heart function, chamber sizes, and valve conditions.
- Cardiac MRI: Offers high-resolution images of cardiac anatomy, tissue characterization (e.g., edema, fibrosis), and precise flow measurements.
- CTA: 3D visualization of coronary arteries and structural anomalies using contrast-enhanced CT scanning.
- Wearable Cardiac Monitors:
- Devices such as Holter monitors, patch ECGs, and smartwatch sensors track heart rate, rhythm, and other cardiac parameters outside clinical settings.
- Innovations include AI-driven arrhythmia detection algorithms and real-time cloud connectivity.
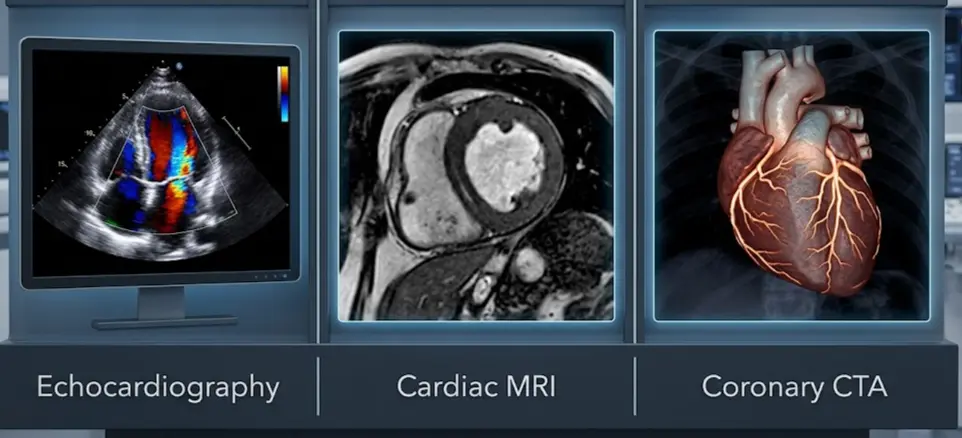
Multimodal cardiovascular imaging: real-time hemodynamic flow assessment via echocardiography Doppler (left), high-contrast tissue characterization through cardiac MRI (center), and 3D volumetric coronary tree reconstruction using contrast-enhanced CTA (right).
Pacemakers and Defibrillators
- Pacemakers:
- Used to correct bradyarrhythmias by delivering timed electrical impulses to maintain proper heart rate.
- Modern systems support rate-responsive pacing and remote monitoring.
- Implantable Cardioverter Defibrillators (ICDs):
- Designed to detect and intervene in life-threatening arrhythmias by delivering high-energy shocks.
- Often combined with pacing capabilities in single, dual, or triple chamber configurations.
- Biventricular Pacemakers (CRT Devices):
- Used in cardiac resynchronization therapy to improve coordination between the left and right ventricles, alleviating heart failure symptoms.
- Devices like the Medtronic Viva XT adapt pacing delays based on daily activity and cardiac electrical signatures.
Applications of Cardiovascular Engineering
Treatment of Coronary Artery Disease (CAD)
- Stents and Angioplasty:
- Engineered stents now include drug-eluting coatings that release antiproliferative agents over time, reducing restenosis.
- Bioresorbable stents are designed to gradually dissolve after supporting vessel healing, eliminating long-term implant risks.
- Advanced balloons with ultrahigh-pressure and cutting-edge materials achieve greater precision in opening blocked arteries.
- Bypass Surgery with Vascular Grafts:
- Improved synthetic graft materials like ePTFE and Dacron now feature heparin or bioactive coatings to reduce thrombosis risk.
- Bioengineered grafts seeded with endothelial cells mimic natural vessels, promoting long-term patency.
- Techniques combining 3D imaging and printing allow patient-specific grafts for better surgical fit and fewer complications.
Management of Heart Failure
- Ventricular Assist Devices (VADs):
- Modern LVADs use magnetic levitation and low-power pumps to minimize blood damage and reduce patient stress.
- Miniaturized RVADs now offer less invasive implantation options and improved durability.
- BiVAD systems coordinate support for both heart chambers, enabling advanced chronic heart failure treatment.
- Artificial Hearts:
- Next-generation total artificial hearts (TAHs) are fully implantable with wireless power transmission and adaptive control systems.
- These devices serve both as a bridge to transplant and as permanent, transplant-free solutions.
- Efforts are underway to improve biomaterials and sensor systems for better size compatibility and responsiveness.
Contemporary AI-Era Computational Paradigms in Cardiovascular Engineering
An artery with an initial radius \(r_1 = 4.0 \text{ mm}\) experiences atherosclerotic plaque deposition that narrows its internal radius to \(r_2 = 2.0 \text{ mm}\). Assuming steady laminar blood flow governed by Hagen-Poiseuille's law (\(R = \frac{8\eta L}{\pi r^4}\)), calculate the exact factor by which vascular flow resistance \(R\) increases across the stenotic segment, and determine the new volumetric flow rate \(Q_2\) if the pressure gradient \(\Delta P\) remains constant at \(80 \text{ mmHg}\) (\(10,665.76 \text{ Pa}\)) with blood viscosity \(\eta = 3.5 \times 10^{-3} \text{ Pa}\cdot\text{s}\) over length \(L = 0.05 \text{ m}\):
$$R = \frac{8 \eta L}{\pi r^4}$$Step 1: Calculate resistance increase factor \(R_2 / R_1\):
$$\frac{R_2}{R_1} = \frac{r_1^4}{r_2^4} = \left(\frac{4.0 \text{ mm}}{2.0 \text{ mm}}\right)^4 = (2.0)^4 = \mathbf{16.0}$$Step 2: Calculate initial resistance \(R_1\) (\(r_1 = 0.004 \text{ m}\)):
$$R_1 = \frac{8 \times (3.5 \times 10^{-3} \text{ Pa}\cdot\text{s}) \times 0.05 \text{ m}}{\pi \times (0.004 \text{ m})^4} = \frac{1.40 \times 10^{-3}}{\pi \times 2.56 \times 10^{-10}} = \frac{1.40 \times 10^{-3}}{8.0425 \times 10^{-10}} = \mathbf{1.7407 \times 10^6 \text{ Pa}\cdot\text{s/m}^3}$$Step 3: Calculate stenotic resistance \(R_2 = 16 \times R_1\):
$$R_2 = 16 \times 1.7407 \times 10^6 = \mathbf{2.785 \times 10^7 \text{ Pa}\cdot\text{s/m}^3}$$Step 4: Compute stenotic volumetric flow rate \(Q_2 = \Delta P / R_2\) (\(\Delta P = 10,665.76 \text{ Pa}\)):
$$Q_2 = \frac{10,665.76 \text{ Pa}}{2.785 \times 10^7 \text{ Pa}\cdot\text{s/m}^3} = 3.8296 \times 10^{-4} \text{ m}^3/\text{s} = \mathbf{22.98 \text{ mL/min}}$$Clinical Physiology Insight: Halving the arterial radius triggers a 16-fold increase in vascular resistance, dropping local blood perfusion drastically. This severe hydraulic constriction explains why mild atherosclerotic plaque progression can precipitate critical myocardial ischemia during physical exertion.
Engineering Trade-offs in Cardiovascular Engineering
| Cardiovascular Design Trade-off | Primary Engineering Benefit | Systemic Penalty / Risk | Quantitative Design Metric |
|---|---|---|---|
| Mechanical Heart Valves vs. Bioprosthetic Tissue Valves | Exceptional mechanical durability; lasts several decades without structural tissue degeneration. | Requires mandatory lifelong systemic anticoagulation therapy (warfarin), elevating hemorrhagic stroke risks. | Implant Lifespan: Mechanical (\(>30 \text{ years}\)); Bioprosthesis (\(10\text{--}15 \text{ years}\)). |
| Drug-Eluting Stents (DES) vs. Bare-Metal Stents (BMS) | Significantly suppresses neointimal proliferation and smooth muscle cell growth, slashing restenosis rates. | Delays endothelialization, requiring prolonged dual antiplatelet therapy (DAPT) to prevent late stent thrombosis. | Restenosis Rate: BMS (\(20\text{--}30\%\)); DES (\(<5\%\)). |
| Continuous-Flow LVADs vs. Pulsatile Total Artificial Hearts | High mechanical reliability, compact size, silent operation, and lower power consumption via magnetic levitation. | Abnormal continuous blood flow dampens native pulse pressure, increasing risks of gastrointestinal arteriovenous malformations. | Pump Durability: Magnetically Levitated LVAD (\(>5\text{ years}\) MTBF). |
| Transcatheter Valve Replacement (TAVR) vs. Open Surgical CABG | Minimally invasive percutaneous delivery avoids sternotomy, cardiopulmonary bypass, and prolonged ICU recovery. | Risk of paravalvular aortic leakage, vascular access site trauma, and potential permanent pacemaker conduction block. | Procedure Recovery Time: TAVR (\(2\text{--}3 \text{ days}\)); Open Surgery (\(7\text{--}10 \text{ days}\)). |
To verify regulatory compliance (ISO 5840), a bioprosthetic heart valve leaflet must undergo accelerated durability bench-testing simulating 15 years of physiological operation, equating to \(N = 1.20 \times 10^9\) total stress cycles at a normal heart rate of 75 bpm. If a specialized test rig cycles at an accelerated frequency of \(f = 15.0 \text{ Hz}\) (\(900 \text{ cycles/minute}\)), calculate the total test duration required in days:
$$\text{Test Duration (Days)} = \frac{N}{f \times 60 \text{ sec/min} \times 1,440 \text{ min/day}} = \frac{1.20 \times 10^9 \text{ cycles}}{15.0 \text{ Hz} \times 86,400 \text{ sec/day}}$$ $$\text{Daily Cycling Capacity} = 15.0 \times 86,400 = 1,296,000 \text{ cycles/day}$$ $$\text{Test Duration} = \frac{1.20 \times 10^9}{1,296,000} = \mathbf{925.93 \text{ days}} \quad (\mathbf{\approx 2.54 \text{ years}})$$Engineering Challenge: Accelerated fatigue testing at 15 Hz exceeds physiological frequencies (1–2 Hz), risking fluid cavitation and unrealistic hydrodynamic stress distribution on biological tissue leaflets, requiring continuous monitoring of hydrodynamic performance parameters throughout the multi-year testing campaign.
Interactive Simulator: Hemodynamic Vessel Flow & Resistance Simulator
Adjust physiological parameters below to simulate arterial pressure drops, fluid shear stress, and flow rates across normal vs. stenotic blood vessels governed by Hagen-Poiseuille hemodynamics.
Interactive runtime environment: https://prep4uni.online/stem/physical-technologies/biomedical-engineering/cardiovascular-engineering/
Emerging Technologies in Cardiovascular Engineering
Bioresorbable Stents
- Definition: Bioresorbable stents are designed to temporarily support narrowed arteries and then gradually dissolve, leaving the vessel in a natural state.
- Advantages:
- Reduces long-term complications such as chronic inflammation or thrombosis.
- Eliminates the risks associated with permanent metallic implants.
- Improves vascular healing and functionality post-dissolution.
- Applications:
- Used in coronary artery disease (CAD) treatment in younger patients requiring future procedures.
- Applied in peripheral arterial disease where long-term flexibility is beneficial.
Smart Cardiovascular Implants
- Definition: These are medical devices with embedded sensors that provide continuous monitoring and real-time data on cardiovascular function.
- Applications:
- Pacemakers and ICDs (Implantable Cardioverter Defibrillators) that adjust output based on patient activity.
- Stents that detect restenosis and send wireless alerts to physicians.
- Benefits:
- Enables proactive management of heart conditions.
- Improves patient outcomes through data-driven, personalized interventions.
Challenges in Cardiovascular Engineering
- Biocompatibility of Implants: One of the foremost challenges in cardiovascular engineering is ensuring that artificial implants—such as stents, pacemakers, and heart valves—are fully biocompatible with human tissues. Materials used in implants must prevent adverse immune reactions, inflammation, or fibrosis, which could lead to device rejection or complications like thrombosis. Innovative surface modifications and bioinert or bioactive coatings are being developed to enhance hemocompatibility and cellular integration.
- Long-Term Durability: Cardiovascular implants are subjected to continuous mechanical stress from the heartbeat and blood flow, demanding exceptional durability and fatigue resistance. Valve leaflets, for instance, must open and close billions of times over the lifespan of the device without structural failure or calcification. Material fatigue, corrosion, and wear over time can lead to device malfunction and necessitate revision surgeries.
- Device Miniaturization: Reducing the size of cardiovascular devices is essential for enabling minimally invasive surgical procedures, especially for pediatric and elderly patients. Miniaturization must be achieved without compromising functionality, signal transmission, or power supply in devices like implantable defibrillators or heart monitors.
- Patient-Specific Solutions: Due to variability in human anatomy and disease progression, a one-size-fits-all approach is often suboptimal. Customizing implants using data from medical imaging and computational modeling allows for more accurate fit and function, though creating bespoke devices introduces manufacturing speed and regulatory challenges.
- Regulatory Approval: Cardiovascular devices undergo rigorous regulatory review to ensure safety, effectiveness, and long-term reliability before clinical use. Developers must generate comprehensive preclinical and clinical data, including biocompatibility testing, in vivo performance, and human trial outcomes.
- Cost and Accessibility: High R&D costs, sophisticated manufacturing processes, and expensive clinical trials contribute to the overall cost of cardiovascular devices, limiting access in low- and middle-income regions.
- Integration with Digital Health Systems: Integrating modern implants securely and seamlessly with electronic health records and telehealth platforms presents challenges in data standardization, interoperability, and cybersecurity.
- Post-Market Surveillance and Recall: Establishing robust post-market surveillance systems is essential for identifying rare long-term complications and coordinating timely recalls.
Future Directions in Cardiovascular Engineering
- Fully Implantable Artificial Hearts: Future innovations aim to produce compact, completely implantable total artificial hearts (TAHs) that eliminate external drivelines using wireless transcutaneous energy transfer systems (TETS).
- Regenerative Cardiovascular Therapies: Stem cell and gene-based approaches lead the charge in regenerating damaged heart tissue post-myocardial infarction using induced pluripotent stem cell (iPSC) derived cardiomyocytes.
- Smart and Connected Implants: IoT-enabled cardiovascular implants will provide continuous real-time data on pressure, flow, and electrophysiology to cloud diagnostic platforms.
- Personalized 3D-Bioprinted Devices: 3D bioprinting utilizing autologous bioinks will produce customized, living vascular grafts and valve scaffolds tailored perfectly to patient anatomy.
- AI-Guided Cardiovascular Surgery: Artificial intelligence algorithms will assist cardiovascular surgeons in real time, optimizing graft placement and robotic catheter navigation.
Frequently Asked Questions
These FAQs connect cardiovascular engineering concepts to hemodynamics, implant design, and clinical care.
Is cardiovascular engineering mainly about devices, or about physiology and modelling as well?
It is all three. Cardiovascular engineers design devices such as stents, valves, and pumps, but they also build mathematical and computational models of blood flow and heart function, working closely with clinicians to understand disease mechanisms.
How is cardiovascular engineering different from general biomedical engineering?
Biomedical engineering covers all organ systems and medical technologies. Cardiovascular engineering focuses specifically on the heart and circulatory system, allowing deeper exploration of hemodynamics, vascular mechanics, and cardiology.
Do I need a strong background in biology to study cardiovascular engineering?
A foundation in physics, mathematics, and basic engineering is key. You will learn cardiovascular anatomy and physiology as you progress, connecting quantitative tools to circulatory mechanics.
What kinds of student projects are common in cardiovascular engineering?
Typical projects include testing small-scale models of heart valves or stents, analyzing ECG waveforms, building mock circulatory flow loops, or running CFD simulations of blood flow in bifurcated arteries.
Is cardiovascular engineering only about invasive implants and surgery?
No. It also encompasses non-invasive diagnostic tools, wearable ECG patches, risk prediction modeling, computational fluid dynamics, and rehabilitation technologies.
Where do cardiovascular engineers typically work after graduation?
Graduates work in medical device firms, imaging software companies, hospital clinical engineering departments, regulatory agencies like the FDA, and research institutes.
Interactive Concept Explorations
Why does blood flow velocity decrease in capillaries despite narrower radii?
What triggers neointimal hyperplasia in stent deployments?
Cardiovascular Engineering Practice Module
Section 1: Foundational Review Questions
1. What primary biological variables serve as inputs in cardiovascular engineering modeling?
2. Define hemodynamics and identify its key governing physical equations.
3. What is the main functional difference between an LVAD and a Total Artificial Heart (TAH)?
4. Why are pyrolytic carbon materials widely selected for mechanical valve leaflets?
5. How does a Drug-Eluting Stent (DES) prevent arterial restenosis compared to a Bare-Metal Stent (BMS)?
6. What advantage do bioprosthetic tissue valves have over mechanical heart valves?
7. Explain how transcatheter aortic valve replacement (TAVR) differs structurally from surgical replacement.
8. What mechanical factors govern wall shear stress (\(\tau\)) in arterial blood vessels?
Section 2: Analytical & Scenario-Based Practice
1. If an arterial stent causes localized flow recirculation and zero wall shear stress regions, what pathological risk develops?
2. Analyze why bioresorbable poly-L-lactic acid (PLLA) stents require thicker struts than cobalt-chromium stents, and evaluate the hydraulic consequences.
3. A patient with an implantable LVAD exhibits elevated serum free hemoglobin. What engineering failure mode does this indicate?
4. Contrast the biomechanical trade-offs between synthetic ePTFE vascular grafts and autologous saphenous vein grafts in small-caliber arterial bypasses.
5. Evaluate how acute changes in blood viscosity (\(\eta\)) impact cardiac workload in patients with polycythemia.
6. Why must finite element analysis (FEA) models for aortic root interventions incorporate anisotropic hyperelastic constitutive equations?
7. Design a diagnostic framework using wearable ECG sensors to distinguish true ventricular arrhythmias from physical motion artifacts.
Section 3: Quantitative Engineering Calculations
1. Arterial Stenosis Vascular Resistance Increase Factor
Problem: An artery with initial radius \(r_1 = 4.0 \text{ mm}\) narrows due to atherosclerosis to \(r_2 = 2.0 \text{ mm}\). Assuming steady laminar flow governed by Poiseuille's law (\(R = \frac{8\eta L}{\pi r^4}\)), calculate the factor by which vascular flow resistance \(R\) increases.
Answer:
Step 1: State the Hagen-Poiseuille resistance equation:
\(R = \frac{8\eta L}{\pi r^4}\)
Step 2: Formulate resistance ratio \(\frac{R_2}{R_1}\):
\(\frac{R_2}{R_1} = \frac{r_1^4}{r_2^4} = \left(\frac{4.0 \text{ mm}}{2.0 \text{ mm}}\right)^4 = (2.0)^4 = \mathbf{16.0}\)
Vascular flow resistance increases by a factor of 16.0.
2. Vascular Graft Volumetric Flow Rate Calculation
Problem: Calculate hydraulic flow rate \(Q\) (in \(\text{mL/s}\)) across a \(0.1 \text{ m}\) graft segment with internal radius \(r = 3.0 \text{ mm}\), blood viscosity \(\eta = 0.0035 \text{ Pa}\cdot\text{s}\), and pressure differential \(\Delta P = 20 \text{ mmHg}\) (\(1 \text{ mmHg} = 133.322 \text{ Pa}\)).
Answer:
Step 1: Convert units to SI (\(r = 0.003 \text{ m}\), \(\Delta P = 20 \times 133.322 = 2,666.44 \text{ Pa}\)):
\(r^4 = (0.003)^4 = 8.1 \times 10^{-11} \text{ m}^4\)
Step 2: Apply Poiseuille equation (\(Q = \frac{\pi \Delta P r^4}{8 \eta L}\)):
\(Q = \frac{\pi \times 2,666.44 \times (8.1 \times 10^{-11})}{8 \times 0.0035 \times 0.1} = \frac{6.784 \times 10^{-7}}{0.0028} = 2.423 \times 10^{-4} \text{ m}^3/\text{s}\)
Step 3: Convert \(\text{m}^3/\text{s}\) to \(\text{mL/s}\) (\(1 \text{ m}^3 = 10^6 \text{ mL}\)):
\(Q = 2.423 \times 10^{-4} \times 10^6 = \mathbf{242.3 \text{ mL/s}}\)
The volumetric flow rate across the graft is 242.3 mL/s.
3. Arterial Wall Shear Stress Calculation
Problem: Determine wall shear stress \(\tau\) (in \(\text{Pa}\)) exerted on an arterial wall of radius \(r = 2.5 \text{ mm}\) under a pressure gradient \(\Delta P / L = 1,500 \text{ Pa/m}\).
Answer:
Step 1: State cylindrical wall shear stress formula:
\(\tau = \left(\frac{\Delta P}{L}\right) \times \left(\frac{r}{2}\right)\)
Step 2: Substitute values (\(r = 0.0025 \text{ m}\)):
\(\tau = 1,500 \times \left(\frac{0.0025}{2}\right) = 1,500 \times 0.00125 = \mathbf{1.875 \text{ Pa}}\)
The wall shear stress exerted on the arterial wall is 1.875 Pa.
4. Cardiac Output Calculation
Problem: A heart beating at \(72 \text{ bpm}\) pumps a stroke volume \(\text{SV} = 70 \text{ mL/beat}\). Calculate Cardiac Output (\(\text{CO}\)) in liters per minute (\(\text{L/min}\)).
Answer:
Step 1: Apply Cardiac Output formula (\(\text{CO} = \text{HR} \times \text{SV}\)):
\(\text{CO} = 72 \text{ beats/min} \times 70 \text{ mL/beat} = 5,040 \text{ mL/min}\)
Step 2: Convert \(\text{mL/min}\) to \(\text{L/min}\):
\(\text{CO} = \frac{5,040 \text{ mL/min}}{1,000} = \mathbf{5.04 \text{ L/min}}\)
The cardiac output is 5.04 L/min.
5. Mean Arterial Pressure (MAP) Calculation
Problem: Systemic Vascular Resistance (\(\text{SVR}\)) is \(1,200 \text{ dynes}\cdot\text{s/cm}^5\) and Cardiac Output is \(5.0 \text{ L/min}\). Calculate Mean Arterial Pressure (\(\text{MAP}\)) assuming Central Venous Pressure (\(\text{CVP}\)) is \(4 \text{ mmHg}\). Note: \(80 \text{ dynes}\cdot\text{s/cm}^5 = 1 \text{ mmHg}\cdot\text{min/L}\).
Answer:
Step 1: Convert SVR to clinical units (\(\text{mmHg}\cdot\text{min/L}\)):
\(\text{SVR} = \frac{1,200}{80} = 15.0 \text{ mmHg}\cdot\text{min/L}\)
Step 2: Apply hemodynamic pressure-flow relationship (\(\text{SVR} = \frac{\text{MAP} - \text{CVP}}{\text{CO}}\)):
\(15.0 = \frac{\text{MAP} - 4.0}{5.0} \Rightarrow \text{MAP} - 4.0 = 75.0 \Rightarrow \text{MAP} = \mathbf{79.0 \text{ mmHg}}\)
The mean arterial pressure is 79.0 mmHg.
6. Accelerated Fatigue Bench-Testing Duration Calculation
Problem: A bioprosthetic valve leaflet undergoes \(1.20 \times 10^9\) stress cycles over 15 years. If test rigs cycle at \(f = 15.0 \text{ Hz}\), calculate accelerated bench-testing time in days required to simulate 15 years of mechanical fatigue.
Answer:
Step 1: Calculate daily stress cycle capacity at \(15.0 \text{ Hz}\):
\(\text{Cycles/Day} = 15.0 \text{ cycles/sec} \times 86,400 \text{ sec/day} = 1,296,000 \text{ cycles/day}\)
Step 2: Compute total test duration in days:
\(\text{Test Duration} = \frac{1.20 \times 10^9 \text{ cycles}}{1,296,000 \text{ cycles/day}} = \mathbf{925.93 \text{ days}}\) (\(\approx 2.54 \text{ years}\))
The accelerated bench-testing duration required is 925.93 days (~2.54 years).
7. Coronary Artery Blood Flow Reynolds Number Calculation
Problem: Estimate Reynolds number (\(\text{Re}\)) for blood flowing through a stenotic coronary artery segment of diameter \(d = 1.5 \text{ mm}\) at mean velocity \(v = 0.8 \text{ m/s}\). Blood density \(\rho = 1,060 \text{ kg/m}^3\) and viscosity \(\eta = 0.0035 \text{ Pa}\cdot\text{s}\). State if flow is laminar or turbulent.
Answer:
Step 1: Apply Reynolds number formula (\(\text{Re} = \frac{\rho v d}{\eta}\)):
\(\text{Re} = \frac{1,060 \times 0.8 \times 0.0015}{0.0035} = \frac{1.272}{0.0035} = \mathbf{363.43}\)
Step 2: Determine flow regime:
Since \(\text{Re} = 363.43 \lt 2,000\), the blood flow remains strictly laminar.
The Reynolds number is 363.43, indicating laminar flow.