
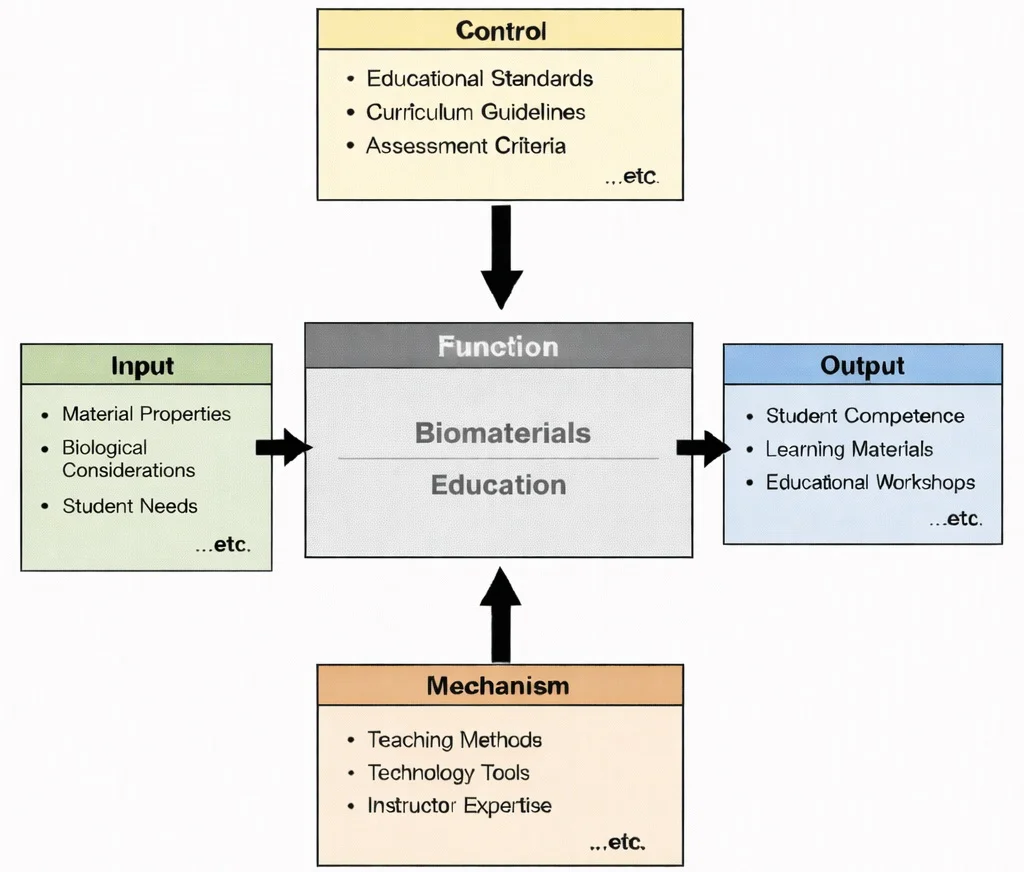
IDEF0 view of Biomaterials Education: material properties and biological needs guided by standards and assessment, enabled by teaching and tools, producing student competence and learning resources.

Biomaterials bridge materials science and medicine to create safe, functional implants and tissue-supporting technologies. This illustration presents biomaterials as an intersection of biology, chemistry, and engineering. A central microscope and laboratory setup are surrounded by molecular networks, cell-like spheres, sample containers, and analytical displays, suggesting research on material composition, biocompatibility, and microstructure. On the left, a skeletal figure and lab vials hint at clinical relevance and testing, while the glowing knee joint on the right points to real-world applications such as implants, coatings, and tissue replacements. Overall, the image conveys how biomaterials are designed, tested, and refined to interact safely with the human body for repair, regeneration, and long-term medical use.
Biomedical Engineering – Knowledge Map
Biomaterials (Current Module)
Centres on creating synthetic and natural substances that function safely within biological environments while maintaining structural integrity, biocompatibility, and controlled degradation.
Rehabilitation Engineering
Applies structural biomaterials design to prosthetic limbs, orthotic devices, and assistive tools that endure repeated cyclical mechanical stress without structural fatigue.
Biomedical Signal Processing
Depends on advanced conductive polymer and bioelectronic interfaces to maintain high signal-to-noise detection across device-tissue boundaries without inflammatory interference.
Medical Imaging
Utilises specialized biocompatible nanoparticles and radiopaque polymeric compounds that enhance anatomical contrast and diagnostic visibility during MRI, CT, and ultrasound scans.
Cardiovascular Engineering
Requires hemocompatible surfaces, eluting bioresorbable polymers, and synthetic graft textiles that resist thrombosis, calcification, and dynamic fluid sheer stresses inside blood vessels.
Neural Engineering
Relies on ultra-soft, flexible hydrogels and conductive micro-arrays capable of long-term biostability and gentle compliance against delicate central nervous system tissue.
Biomechanics
Establishes physiological stress distributions, wear mechanics, and kinematic loading equations that govern biomaterial selection for orthopedic implants and bone plates.
Tissue Engineering & Regenerative Medicine
Uses porous 3D ECM-mimicking scaffolds to foster cellular adhesion, proliferation, vascularization, and eventual replacement by native extracellular matrix components.
Bioinformatics
Provides structural simulation algorithms and molecular docking models to predict protein adsorption, cellular signaling responses, and toxicity at the biomaterial surface.
Pharmaceutical Engineering
Integrates responsive polymers and bioresorbable micro-encapsulations to regulate drug diffusion kinetics, targeted payload delivery, and localized therapeutic release profiles.
Clinical Engineering
Manages hospital deployment, sterilisation protocols, post-market risk assessments, and regulatory compliance standards governing patient-contact biomaterial hardware.
Biomedical Engineering – Overview
Connects biomaterials research to the overarching multidisciplinary framework integrating medicine, physical science, and technology to optimize human healthcare outcomes.
Core Properties of Biomaterials
Biocompatibility
- Definition: Biocompatibility refers to the ability of a biomaterial to perform its desired function within the human body without eliciting adverse reactions such as toxicity, inflammation, immunological rejection, or carcinogenicity. This property is critical for ensuring that the material remains inert or beneficial when in contact with biological tissues.
- Importance: A lack of biocompatibility can lead to chronic inflammation, fibrosis, or device failure. For instance, metallic implants like titanium alloys are favored due to their minimal reactivity with tissues. Polymers such as polylactic acid (PLA) are engineered to degrade safely and avoid long-term immune response. Rigorous in vitro and in vivo testing is required to evaluate cytotoxicity, hemocompatibility, and histocompatibility before clinical use.
- Factors Affecting Biocompatibility: Material composition, surface chemistry, degradation by-products, and interaction with the host immune system all influence biocompatibility. Tailoring surface coatings, such as heparinization or PEGylation, can improve compatibility and reduce protein adsorption or clotting.
Mechanical Properties
- Definition: Mechanical properties encompass a range of attributes such as tensile strength, compressive strength, Young’s modulus, elongation at break, hardness, fracture toughness, and fatigue resistance. These characteristics determine how a biomaterial responds to mechanical stress and strain.
- Importance: For applications in orthopedics or cardiovascular implants, matching the mechanical properties of native tissues is essential. Bone implants must support body weight and cyclic loading without fracturing or deforming. Stents used in arteries require flexibility and strength to expand and maintain lumen patency. Failure to meet mechanical requirements can result in device collapse, wear, or tissue damage.
- Testing Methods: Mechanical testing involves standardized procedures such as tensile, compression, and fatigue testing under simulated physiological conditions. Finite element analysis (FEA) is also used to model stress distribution and optimize device design.
Bioactivity
- Definition: Bioactivity is the ability of a material to induce a specific biological response at the interface of the material, resulting in the formation of a bond between the tissue and the material. Unlike inert biomaterials, bioactive ones engage in cellular signaling and tissue regeneration.
- Importance: Materials like bioactive glass and hydroxyapatite promote bone regeneration by forming a calcium phosphate layer that bonds with native bone. Bioactive surfaces can also encourage stem cell differentiation or endothelialization in vascular grafts. In tissue engineering, scaffold bioactivity determines the quality and rate of tissue integration.
- Advancements: Functionalization of surfaces with peptides, growth factors, or extracellular matrix (ECM) proteins enhances bioactivity. Responsive biomaterials that release bioactive agents in response to environmental cues (e.g., pH or temperature) are under active development.
Degradability / Biodegradability
- Definition: Degradable biomaterials are designed to break down within the body into non-toxic byproducts that can be metabolized or excreted. This can occur through hydrolysis, enzymatic action, or oxidative mechanisms.
- Importance: Biodegradable materials eliminate the need for secondary surgical removal, reducing patient risk and cost. This is especially crucial in temporary applications such as sutures, wound dressings, drug delivery capsules, and resorbable scaffolds. The degradation rate must be matched to tissue healing time or therapeutic duration to avoid premature failure or prolonged residue.
- Examples and Materials: Common biodegradable polymers include polyglycolic acid (PGA), PLA, polycaprolactone (PCL), and collagen. Recent innovations include hybrid degradable-inorganic composites and bioresorbable metals like magnesium alloys for orthopedic and vascular uses.
Surface Properties
- Definition: Surface properties refer to the topography, roughness, wettability, porosity, surface energy, and chemical functionality of a biomaterial's external layer. These attributes directly influence cell adhesion, protein adsorption, bacterial colonization, and immune response.
- Importance: A material’s surface can dictate whether cells proliferate and differentiate or whether inflammation and fibrous encapsulation occur. For example, titanium implants with roughened or nano-patterned surfaces show improved osseointegration compared to smooth surfaces. Hydrophilic surfaces tend to favor tissue compatibility, whereas hydrophobic ones may resist biofouling.
- Surface Modification Techniques: Plasma treatment, self-assembled monolayers (SAMs), layer-by-layer coatings, and laser patterning are among the techniques used to tailor surface properties. Advances in surface nanotopography aim to mimic natural ECM structures to guide cell behavior.
Additional Core Properties
Chemical Stability
Processability and Manufacturability
Sterilizability
Cost and Accessibility
Types of Biomaterials
Metallic Biomaterials
- Common Materials: Stainless steel (316L), titanium and its alloys (e.g., Ti-6Al-4V), cobalt-chromium alloys, tantalum.
- Physical and Mechanical Properties: Exceptional strength, high fatigue and wear resistance, excellent corrosion resistance especially in physiological environments, and favorable machinability.
- Surface Engineering: Techniques such as anodization, plasma spraying, and hydroxyapatite coating are often applied to improve osseointegration and reduce ion release.
- Biocompatibility Considerations: While highly durable, some alloys may release metal ions (e.g., nickel or cobalt) that could elicit allergic or toxic responses in certain individuals, necessitating careful material selection.
- Applications:
- Orthopedic devices: Total hip arthroplasties, knee replacements, spinal fusion hardware
- Dental implants: Titanium fixtures due to osseointegration capability
- Cardiovascular applications: Vascular stents, artificial heart valves, and pacemaker casings
- Fracture fixation: Plates, rods, and screws
Ceramic Biomaterials
- Common Materials: Alumina (\(\text{Al}_2\text{O}_3\)), zirconia (\(\text{ZrO}_2\)), hydroxyapatite (\(\text{HA}\)), tricalcium phosphate (\(\text{TCP}\)), and bioglass.
- Unique Properties: High hardness and compressive strength, minimal wear, excellent chemical inertness, and favorable compatibility with bone tissue.
- Limitations: Brittle nature makes them susceptible to sudden fracture under tensile or shear stress, limiting their use in load-bearing implants without careful design.
- Bioactive Behavior: Certain ceramics like HA and bioglass are osteoconductive and promote direct bonding to bone.
- Applications:
- Bone substitutes and grafts: Especially in maxillofacial and spinal surgeries
- Dental restorations: Crowns, inlays, and bridges due to excellent aesthetics and durability
- Joint prosthetics: Ceramic-on-ceramic bearing surfaces in hip replacements for reduced wear debris
Polymeric Biomaterials
- Common Materials: Polyethylene (PE), polylactic acid (PLA), polyglycolic acid (PGA), poly(lactic-co-glycolic acid) (PLGA), polymethyl methacrylate (PMMA), polycaprolactone (PCL), polyurethane, and silicone elastomers.
- Design Versatility: Can be tailored in terms of porosity, degradation rates, elasticity, and drug-loading capacity.
- Biodegradable Polymers: PLA, PGA, and PLGA break down into lactic and glycolic acid, which are metabolized by the body—useful in temporary implants and drug delivery.
- Non-Degradable Polymers: PE and PMMA are ideal for permanent implants and hard-tissue applications like bone cement.
- Applications:
- Sutures and surgical meshes
- Wound dressings with antimicrobial or oxygen-releasing properties
- Scaffolds for tissue regeneration
- Controlled drug delivery systems such as nanoparticles and hydrogels
Natural Biomaterials
- Common Materials: Collagen, fibrin, gelatin, alginate, chitosan, silk fibroin, and hyaluronic acid.
- Source and Origin: Derived from animal or microbial origins, these materials are often highly similar to human extracellular matrix components.
- Advantages: Naturally recognized by the body, low immunogenicity, support for cell attachment, proliferation, and differentiation.
- Challenges: Batch variability, possible pathogen transmission, and lower mechanical strength compared to synthetic alternatives.
- Applications:
- Scaffolds for skin, cartilage, and nerve tissue regeneration
- Hemostatic agents and wound dressings
- Drug delivery systems using microencapsulation
- Injectable hydrogels for minimally invasive therapies
Composite Biomaterials
- Definition: Materials formed by combining two or more constituents—often from different categories (e.g., metal-polymer or ceramic-polymer)—to achieve synergistic properties.
- Mechanical Optimization: Incorporating ceramics into polymers improves compressive strength; adding polymers to metals enhances flexibility and reduces stress shielding.
- Biofunctional Design: Nanocomposites can be engineered for smart responses to pH, temperature, or enzymatic activity—ideal for targeted drug delivery or dynamic tissue scaffolds.
- Applications:
- Orthopedic and dental implants with enhanced bioactivity
- Bone cements with improved fatigue resistance
- Multifunctional scaffolds for cartilage and tendon regeneration
Emerging Categories of Biomaterials
- Smart Biomaterials: Designed to respond to stimuli such as light, magnetic fields, pH, or temperature. Useful in responsive drug release and dynamic tissue scaffolds.
- Self-Healing Biomaterials: Capable of autonomously repairing damage, extending implant longevity.
- Conductive Biomaterials: Used in bioelectronic interfaces and neural engineering to transmit electrical signals safely between tissues and devices.
Applications of Biomaterials
Implants and Prosthetics
Tissue Engineering and Regenerative Medicine
Drug Delivery Systems
Wound Healing and Dressings
Cardiovascular Applications
Ophthalmology
Emerging Fields
Contemporary AI-Era Computational Paradigms in Biomaterials Science
A porous poly(lactic-co-glycolic acid) (PLGA 50:50) tissue engineering scaffold undergoes bulk hydrolytic ester cleavage in physiological saline (\(\text{pH } 7.4\), \(37.0^\circ\text{C}\)). The initial mass of the scaffold is \(M_0 = 250.0 \text{ mg}\), and its number-average molecular weight is \(\bar{M}_{n,0} = 60,000 \text{ g/mol}\). Assuming first-order degradation kinetics:
$$M(t) = M_0 \exp(-k_d t), \quad t_{1/2} = \frac{\ln(2)}{k_d}$$where empirical hydrolysis rate constant \(k_d = 0.087 \text{ day}^{-1}\). Calculate the scaffold degradation half-life \(t_{1/2}\) in days, determine the remaining scaffold mass \(M(14)\) after 14 days of implantation, and calculate the cumulative mass percentage lost:
Step 1: Compute polymer degradation half-life (\(t_{1/2}\)):
$$t_{1/2} = \frac{\ln(2)}{k_d} = \frac{0.693147}{0.087 \text{ day}^{-1}} = \mathbf{7.97 \text{ days}}$$Step 2: Evaluate exponential decay term at \(t = 14.0 \text{ days}\):
$$-k_d \cdot t = -0.087 \text{ day}^{-1} \times 14.0 \text{ days} = -1.218$$ $$\exp(-1.218) \approx 0.29582$$Step 3: Calculate remaining scaffold mass \(M(14)\):
$$M(14) = 250.0 \text{ mg} \times 0.29582 = \mathbf{73.95 \text{ mg}}$$Step 4: Compute cumulative mass percentage lost to cellular surroundings:
$$\text{Mass Lost} = 250.0 \text{ mg} - 73.95 \text{ mg} = 176.05 \text{ mg}$$ $$\% \text{ Loss} = \left(\frac{176.05 \text{ mg}}{250.0 \text{ mg}}\right) \times 100 = \mathbf{70.42\%}$$Biomaterials Engineering Note: Bulk eroding polymers like PLGA 50:50 maintain overall scaffold geometric boundaries while internal ester linkages rapidly cleave, causing an accumulation of lactic and glycolic acid monomers that can lower localized microenvironmental pH if vascular clearance is insufficient.
Engineering Trade-offs in Biomaterials Design
| Biomaterial Design Trade-off | Primary Engineering Benefit | Systemic Penalty / Risk | Quantitative Design Metric |
|---|---|---|---|
| Titanium Alloy (Ti-6Al-4V) vs. Cobalt-Chromium (CoCr) Implants | Lower Young's modulus (\(E \approx 110 \text{ GPa}\)) mitigates stress shielding compared to CoCr (\(E \approx 220 \text{ GPa}\)). | Lower hardness and inferior wear resistance; prone to fretting wear if used as an un-coated articulating joint. | Yield Strength: Ti-6Al-4V (\(\ge 860 \text{ MPa}\)); CoCr (\(\ge 500\text{--}800 \text{ MPa}\)). |
| Alumina / Zirconia Ceramics vs. UHMWPE Bearing Surfaces | Ultra-low friction coefficient and negligible volumetric wear rate in total hip arthroplasty. | Low fracture toughness; susceptible to sudden catastrophic brittle fracture under high impact loading. | Fracture Toughness: Alumina (\(K_{1c} \approx 3\text{--}4 \text{ MPa}\cdot\text{m}^{1/2}\)); UHMWPE (\(\approx 8\text{--}10 \text{ MPa}\cdot\text{m}^{1/2}\)). |
| Rapid Hydrolytic Degradation (PLGA 50:50) vs. Slow Degradation (PCL) | Rapid clearance (\(6\text{--}8 \text{ weeks}\)) eliminates long-term foreign body presence in temporary healing applications. | Rapid mass loss causes sudden mechanical strength collapse and acidic degradation byproduct accumulation. | Degradation Half-Life: PLGA 50:50 (\(\approx 1\text{--}2 \text{ months}\)); PCL (\(\approx 2\text{--}3 \text{ years}\)). |
| High Porosity (\(\Pi \ge 80\%\)) vs. Low Porosity (\(\Pi \le 40\%\)) Scaffolds | Maximizes surface area for cellular infiltration, vascular neovascularization, and nutrient diffusion. | Dramatic loss of compressive load-bearing capability following Gibson-Ashby cellular mechanics. | Gibson-Ashby Scaling: Compressive Modulus \(E^* \approx E_s (1 - \Pi)^2\). |
Tissue engineering scaffolds for trabecular bone repair must provide interconnected porosity (\(\Pi\)) for capillary ingrowth while maintaining compressive modulus \(E^*\) comparable to native cancellous bone (\(0.1\text{ to }1.0 \text{ GPa}\)). Using the Gibson-Ashby cellular solids open-cell scaling law:
$$\frac{E^*}{E_s} = C \left(1 - \Pi\right)^2$$where solid hydroxyapatite ceramic strut modulus \(E_s = 80.0 \text{ GPa}\) and dimensionless geometric constant \(C = 1.0\). Calculate the effective compressive modulus \(E^*\) when scaffold porosity is engineered at (a) \(\Pi = 60.0\%\) (\(0.60\)) versus (b) \(\Pi = 85.0\%\) (\(0.85\)):
Step 1: Case A - Porosity \(\Pi = 0.60\) (Relative density \(\rho^*/\rho_s = 0.40\)):
$$E^*_{60\%} = 80.0 \text{ GPa} \times (1 - 0.60)^2 = 80.0 \text{ GPa} \times (0.40)^2 = 80.0 \times 0.16 = \mathbf{12.80 \text{ GPa}}$$Step 2: Case B - Porosity \(\Pi = 0.85\) (Relative density \(\rho^*/\rho_s = 0.15\)):
$$E^*_{85\%} = 80.0 \text{ GPa} \times (1 - 0.85)^2 = 80.0 \text{ GPa} \times (0.15)^2 = 80.0 \times 0.0225 = \mathbf{1.80 \text{ GPa}}$$Biomaterial Selection Insight: Increasing porosity from 60% to 85% drops structural stiffness by 86%, demonstrating the strict compromise between biological transport space and structural load-bearing capacity.
Interactive Biomaterial Stress-Strain & Degradation Simulator
Stress-Strain Response Curve
In Vivo Degradation Profile (Mass Remaining)
Interactive runtime environment: https://prep4uni.online/stem/physical-technologies/biomedical-engineering/biomaterials/
Emerging Trends in Biomaterials
Smart Biomaterials
- Definition: Materials that respond dynamically to environmental stimuli (e.g., changes in temperature, pH, enzymatic concentration, or mechanical stress).
- Applications:
- Self-healing orthopedic coatings and smart bio-implants.
- Closed-loop drug delivery systems (e.g., glucose-responsive insulin release).
Nanostructured Biomaterials
- Definition: Materials engineered at the nanoscale (1–100 nm) to optimize surface energy and cell-receptor interactions.
- Applications:
- Targeted intracellular cancer therapeutics.
- Electrospun nanofiber scaffolds mimicking collagen fibrils for tissue regeneration.
Bioactive and Bioinspired Materials
- Definition: Materials designed to actively engage in cellular signaling, promote tissue integration, or mimic biological architectures (e.g., nacre, mussel adhesive proteins).
- Applications:
- Osteoinductive bone grafts that stimulate rapid osteogenesis.
- Non-fouling surfaces that resist bacterial colonization and biofouling.
3D Bioprinting
- Definition: Layer-by-layer robotic deposition of hydrogels and living cellular spheroids (bioinks) into complex anatomical geometry.
- Applications:
- Patient-specific anatomical tissue constructs and osteochondral grafts.
- Organ-on-a-chip models for pharmacological screening.
Biodegradable Implants
- Definition: Transient implants designed to support tissue healing and subsequently resorb completely into non-toxic metabolizable end-products.
- Applications:
- Bioresorbable coronary stents and orthopedic bone fixation hardware.
Challenges in Biomaterials Development
1. Long-Term Biocompatibility & Immune Evasion
Preventing chronic foreign-body reaction, fibrous capsule formation, and immune-mediated degradation remains a primary challenge for permanent implants.
2. Mechanical Matching & Stress Shielding
Ensuring stiff metallic implants do not absorb physiological loads completely away from adjacent bone, which causes localized bone resorption (osteopenia) and device loosening.
3. Infection Risks & Biofilm Formation
Bacterial adhesion on implant surfaces leads to protective biofilm formation, rendering conventional antibiotic treatments ineffective and necessitating surgical revision.
4. Stringent Regulatory Approvals
Navigating rigorous FDA/EMA multi-phase clinical trial requirements, device classification hurdles, and standardized ISO 10993 toxicity evaluations.
5. Scalable Manufacturing & Cost Accessibility
Translating complex laboratory synthesis procedures (e.g., nano-patterning or bioprinting) into cost-effective, cGMP-compliant industrial manufacturing processes.
Future Directions in Biomaterials
Personalized Patient-Specific Implants
Utilizing CT/MRI volumetric medical scans to additive-manufacture (3D print) customized porous titanium and ceramic implants tailored to complex patient anatomy.
Biofabrication of Whole Organs
Combining induced pluripotent stem cells (iPSCs) with advanced vascularized bioinks to print functional, immunologically matched visceral organ structures.
Electronic & Sensor Integration
Embedding micro-sensors directly within bio-scaffolds to wirelessly stream real-time physiological metrics such as strain, pH, infection markers, and temperature.
Sustainable & Green Biomaterials
Developing biopolymers sourced from eco-friendly bio-refineries (e.g., chitin, alginate, marine collagen) to lower environmental manufacturing footprints.
Why Study Biomaterials
Designing Materials for the Human Body
Biomaterials are specially engineered to interact with biological systems. Students learn to develop materials used in implants, prosthetics, and tissue scaffolds. These materials must be safe, durable, and compatible with the body.
Biocompatibility and Safety
Understanding immune responses, toxicity, and material degradation is key. Students study how to evaluate and test materials for long-term safety. This ensures that devices perform reliably inside the body.
Applications in Regenerative Medicine
Biomaterials play a critical role in healing and regeneration. Students learn to design materials that support cell growth and tissue repair. This leads to advances in wound healing, bone repair, and organ regeneration.
Interdisciplinary Innovation
The field combines chemistry, biology, materials science, and engineering. Students are encouraged to innovate at the intersection of disciplines. This leads to the development of novel medical technologies.
Industry and Research Opportunities
Graduates can work in biomedical companies, hospitals, or academic labs. They help create next-generation implants and drug delivery systems. Biomaterials engineering is essential to the future of healthcare.
Biomaterials: Conclusion
Empowering a New Era of Personalized Medicine
Driving Innovation in Regenerative Therapies
Enhancing Longevity and Quality of Life
Smart and Responsive Systems
Biomaterials Beyond Medicine
Challenges and Ethical Considerations
Future Directions and Multidisciplinary Integration
A Lasting Impact
Frequently Asked Questions on Biomaterials
Why do engineers spend so much effort choosing “just the material” for a medical device?
In a medical device, the material is not “just” a background detail; it is what the patient’s body meets every day. The choice of material determines how strong the device is, how long it lasts, how the immune system reacts, and even how bacteria or proteins attach to it. A good material choice can mean a joint replacement that quietly works for decades, while a poor choice can lead to pain, infection, or early device failure.
How is a biomaterial different from an ordinary engineering material?
Many biomaterials start life as familiar engineering materials—metals, polymers, ceramics—but they are used in a very demanding environment: the human body. Unlike a bridge or a car, an implant must coexist with cells, blood, and immune responses. This means that issues such as toxicity, corrosion in body fluids, protein adsorption, and long-term tissue response are as important as strength or stiffness.
Why are there so many different biomaterials instead of one “perfect” option?
No single material can satisfy all requirements for every application. A hip joint, a heart valve, a dissolvable suture, and a soft contact lens all face different mechanical loads, time scales, and tissue environments. Engineers therefore build a toolkit of metals, polymers, ceramics, and composites, each tuned for a particular task, and sometimes combine them in layered or hybrid designs.
What does it mean when a biomaterial is called “bioinert” or “bioactive”?
A bioinert material aims to cause as little reaction as possible: the body tends to form a stable capsule around it, and the device quietly does its job. A bioactive material, by contrast, is designed to interact more directly with tissue—for example, stimulating bone growth or releasing ions that encourage healing. Both strategies can be useful, depending on whether we want the body to “ignore” the implant or actively integrate with it.
How do biomaterials connect to areas like tissue engineering and regenerative medicine?
In tissue engineering, biomaterials often act as scaffolds that guide cells to grow, organise, and eventually form functional tissue. The scaffold must provide mechanical support, allow nutrients to pass, and gradually degrade as new tissue takes over. Regenerative medicine depends heavily on such smart materials, which not only occupy space but also send biochemical and mechanical signals to cells.
Are biomaterials only used inside the body?
Many biomaterials are implanted, but others work at the body’s surface or in contact with bodily fluids outside the body. Examples include wound dressings that promote healing, dialysis membranes that filter blood, or lab-on-a-chip devices that analyse tiny samples. In all these cases the material still has to interact safely with cells and molecules, even if it is not permanently implanted.
What should a student pay attention to when first learning about biomaterials?
It helps to keep three questions in view: What does this material do mechanically? How does the body react to it over hours, months, and years? And how might it fail? Linking these questions to real clinical examples—successful implants and well-documented failures—makes the subject much easier to remember and prepares you for deeper study in biomedical engineering.
Interactive Concept Review Exercises
Review Question 1: What defines a material as a "biomaterial"?
Review Question 2: Why is titanium preferred for load-bearing dental and orthopedic implants?
Review Question 3: How do synthetic biodegradable polymers like PLGA degrade inside the body?
End-of-Page Comprehensive Practice Module
Section 1: Foundational Review Questions
1. What are biomaterials, and how are they used in biomedical engineering?
2. What are the four main classes of biomaterials, and what is a typical use for each class?
3. What does biocompatibility mean, and why is it context-dependent?
4. How do surface properties of biomaterials influence biological responses?
5. What is the difference between biodegradable and non-biodegradable biomaterials?
6. How do mechanical properties such as Young's modulus influence material selection?
7. What are some common clinical applications of biomaterials in cardiovascular medicine?
8. Why is corrosion resistance critical for metallic biomaterials?
Section 2: Analytical & Scenario-Based Thought Questions
1. An orthopedic surgeon notes bone loss (osteopenia) surrounding a stiff metallic hip stem. Explain the bio-mechanical phenomenon occurring and how biomaterials engineering solves it.
2. Compare the hemocompatibility challenges of a permanent mechanical heart valve versus a bioresorbable coronary stent.
3. Why are ceramic biomaterials ideal for hip joint bearing surfaces, but unsuitable for bone fixation plates?
4. How does the surface energy and wettability (hydrophilic vs. hydrophobic) of a polymer impact protein adsorption upon blood contact?
5. In tissue engineering, what happens if the scaffold degradation rate is significantly faster than the rate of cell extracellular matrix (ECM) deposition?
6. Why do hydrogels exhibit physical properties closely resembling soft biological tissues, and what limits their use in orthopedics?
7. How can nanostructured surface features on an implant reduce bacterial infection without using antibiotic drugs?
Section 3: Numerical Problems & Step-by-Step Solutions
1. Titanium Bone Implant Tensile Stress and Elongation Calculation
Problem: A cylindrical bone implant with initial length \(L_0 = 80.0 \text{ mm}\) and diameter \(d = 10.0 \text{ mm}\) is subjected to a tensile force \(F = 5,000.0 \text{ N}\). If the material's Young's Modulus is \(E = 100.0 \text{ GPa}\), calculate the tensile stress (\(\sigma\)) in \(\text{MPa}\) and total elongation (\(\Delta L\)) in \(\text{mm}\).
Answer:
Step 1: Calculate Cross-Sectional Area (\(A\)):
\(A = \frac{\pi}{4} d^2 = 0.785398 \times (10.0 \text{ mm})^2 = 78.5398 \text{ mm}^2 = 7.854 \times 10^{-5} \text{ m}^2\)
Step 2: Calculate Tensile Stress (\(\sigma = \frac{F}{A}\)):
\(\sigma = \frac{5,000.0 \text{ N}}{78.5398 \text{ mm}^2} = \mathbf{63.66 \text{ MPa}}\)
Step 3: Calculate Strain (\(\varepsilon\)) using Hooke's Law (\(\sigma = E \cdot \varepsilon\)):
\(E = 100.0 \text{ GPa} = 100,000.0 \text{ MPa}\)
\(\varepsilon = \frac{\sigma}{E} = \frac{63.66 \text{ MPa}}{100,000.0 \text{ MPa}} = 0.0006366\)
Step 4: Calculate Total Elongation (\(\Delta L = \varepsilon \cdot L_0\)):
\(\Delta L = 0.0006366 \times 80.0 \text{ mm} = \mathbf{0.0509 \text{ mm}}\)
The tensile stress is 63.66 MPa and the total elongation is 0.0509 mm.
2. Biodegradable PLGA Scaffold First-Order Hydrolytic Mass Loss
Problem: A biodegradable PLGA scaffold degrades via first-order kinetics: \(M(t) = M_0 \cdot \exp(-k_d t)\). Initial mass \(M_0 = 250.0 \text{ mg}\) and degradation constant \(k_d = 0.087 \text{ day}^{-1}\). Calculate polymer half-life (\(t_{1/2}\)) and remaining scaffold mass after \(14.0 \text{ days}\).
Answer:
Step 1: Calculate Half-Life (\(t_{1/2} = \frac{\ln(2)}{k_d}\)):
\(t_{1/2} = \frac{0.693147}{0.087 \text{ day}^{-1}} = \mathbf{7.97 \text{ days}}\)
Step 2: Calculate Mass at \(t = 14.0 \text{ days}\):
\(M(14) = 250.0 \text{ mg} \times \exp(-0.087 \times 14) = 250.0 \times \exp(-1.218) \approx 250.0 \times 0.29582 = \mathbf{73.95 \text{ mg}}\)
The scaffold half-life is 7.97 days, and the remaining mass at Day 14 is 73.95 mg.
3. Fickian Diffusion Drug Release from Spherical Nanoparticles
Problem: A spherical drug delivery nanoparticle of radius \(R = 100.0 \text{ nm}\) releases therapeutic molecules governed by Fickian diffusion: \(\frac{M_t}{M_\infty} = 4 \left( \frac{D t}{\pi R^2} \right)^{0.5}\). If diffusion coefficient \(D = 1.0 \times 10^{-18} \text{ cm}^2/\text{s}\), calculate the fraction of drug released after \(t = 3,600.0 \text{ seconds}\).
Answer:
Step 1: Convert radius to cm and compute \(R^2\):
\(R = 100.0 \text{ nm} = 1.0 \times 10^{-5} \text{ cm}\)
\(R^2 = 1.0 \times 10^{-10} \text{ cm}^2\)
Step 2: Compute term inside square root (\(\frac{D t}{\pi R^2}\)):
\(\text{Numerator} = 1.0 \times 10^{-18} \text{ cm}^2/\text{s} \times 3,600.0 \text{ s} = 3.60 \times 10^{-15} \text{ cm}^2\)
\(\text{Denominator} = \pi \times 1.0 \times 10^{-10} \text{ cm}^2 \approx 3.14159 \times 10^{-10} \text{ cm}^2\)
\(\text{Ratio} = \frac{3.60 \times 10^{-15}}{3.14159 \times 10^{-10}} = 1.14592 \times 10^{-5}\)
Step 3: Evaluate square root and calculate release fraction:
\(\sqrt{1.14592 \times 10^{-5}} \approx 0.0033851\)
\(\frac{M_t}{M_\infty} = 4 \times 0.0033851 = 0.01354 = \mathbf{1.35\%}\)
The cumulative drug release fraction after 1 hour is 1.35%.
4. Porous Hydroxyapatite Bone Scaffold Density & Porosity Evaluation
Problem: A porous hydroxyapatite bone scaffold has a solid strut density \(\rho_{\text{solid}} = 3.16 \text{ g/cm}^3\). A scaffold cube of dimensions \(2.0 \text{ cm} \times 2.0 \text{ cm} \times 2.0 \text{ cm}\) has a measured dry mass of \(10.11 \text{ g}\). Calculate bulk density (\(\rho_{\text{bulk}}\)) and percentage porosity (\(\Pi\)).
Answer:
Step 1: Calculate total scaffold volume (\(V_{\text{total}}\)):
\(V_{\text{total}} = 2.0 \text{ cm} \times 2.0 \text{ cm} \times 2.0 \text{ cm} = 8.0 \text{ cm}^3\)
Step 2: Calculate bulk density (\(\rho_{\text{bulk}} = \frac{M}{V_{\text{total}}}\)):
\(\rho_{\text{bulk}} = \frac{10.11 \text{ g}}{8.0 \text{ cm}^3} = \mathbf{1.264 \text{ g/cm}^3}\)
Step 3: Calculate percentage porosity (\(\Pi = \left[ 1 - \frac{\rho_{\text{bulk}}}{\rho_{\text{solid}}} \right] \times 100\%\)):
\(\frac{\rho_{\text{bulk}}}{\rho_{\text{solid}}} = \frac{1.264}{3.16} = 0.400\)
\(\Pi = (1 - 0.400) \times 100\% = \mathbf{60.0\%}\)
The bulk density is 1.264 g/cm³ with a porosity of 60.0%.
5. Titanium Dental Implant Fatigue Wöhler Stress Amplitude Calculation
Problem: A titanium dental implant undergoes cyclic fatigue testing, failing after \(N = 5.0 \times 10^5 \text{ cycles}\). If the baseline Wöhler S-N fatigue curve equation for this titanium alloy is \(S = 1,200.0 \cdot N^{-0.08}\) (where \(S\) is stress amplitude in \(\text{MPa}\)), determine the applied stress amplitude \(S\).
Answer:
Step 1: Compute \(N^{-0.08}\) for \(N = 500,000\):
\(\ln(500,000) = 13.12236\)
\(\text{Exponent} = -0.08 \times 13.12236 = -1.049789\)
\(\exp(-1.049789) \approx 0.35001\)
Step 2: Calculate stress amplitude (\(S\)):
\(S = 1,200.0 \times 0.35001 = \mathbf{420.01 \text{ MPa}}\)
The fatigue stress amplitude sustained by the implant is 420.0 MPa.
6. Bioresorbable Magnesium Orthopedic Screw In Vivo Degradation Rate
Problem: A bioresorbable magnesium orthopedic screw weighing \(1.20 \text{ g}\) degrades uniformly in simulated body fluid at a steady rate of \(0.015 \text{ g/day}\) over a \(30\)-day period. Calculate total mass lost and percentage of initial mass remaining.
Answer:
Step 1: Calculate total mass lost in 30 days:
\(\text{Mass Lost} = 0.015 \text{ g/day} \times 30 \text{ days} = \mathbf{0.450 \text{ g}}\)
Step 2: Calculate remaining mass:
\(\text{Mass Remaining} = 1.20 \text{ g} - 0.450 \text{ g} = \mathbf{0.750 \text{ g}}\)
Step 3: Calculate percentage remaining:
\(\% \text{ Remaining} = \left(\frac{0.750 \text{ g}}{1.20 \text{ g}}\right) \times 100 = \mathbf{62.50\%}\)
The screw loses 0.45 g with 62.5% of its original mass remaining.
7. Polymeric Micro-Sphere Drug Loading Concentration
Problem: A polymeric drug delivery micro-sphere has a total volume \(V = 4.19 \times 10^{-6} \text{ cm}^3\) and contains \(0.85 \text{ mg}\) of an anti-inflammatory drug payload. Calculate the volumetric drug loading concentration (\(C\)) in \(\text{mg/cm}^3\).
Answer:
Step 1: Apply volumetric concentration formula (\(C = \frac{\text{Mass}}{\text{Volume}}\)):
\(C = \frac{0.85 \text{ mg}}{4.19 \times 10^{-6} \text{ cm}^3} = 202,863.96 \text{ mg/cm}^3\)
Step 2: Express in standard scientific notation:
\(C = \mathbf{2.03 \times 10^5 \text{ mg/cm}^3}\)
The drug loading concentration is 2.03 × 10⁵ mg/cm³.