
Medical Imaging Education, as shown in this IDEF0 diagram, functions as a structured transformation that turns raw imaging Inputs into dependable clinical understanding. Students begin with Inputs such as scan data and patient imagery—visual information that can only be useful when it is acquired correctly and interpreted with discipline. Their learning is guided by Controls like safety standards and image quality protocols, which shape how imaging is performed (protecting patients and operators) and how images are judged (ensuring clarity, consistency, and diagnostic reliability). The transformation is enabled by Mechanisms such as imaging equipment and processing software, through which learners practice the full workflow: acquisition choices, parameter settings, reconstruction, enhancement, artifact recognition, and validation. The Outputs are the capabilities that matter in real settings—interpretation skills and diagnostic abilities—so graduates can read images with care, recognize what is normal versus concerning, communicate findings accurately, and understand how technical decisions upstream affect clinical meaning downstream.
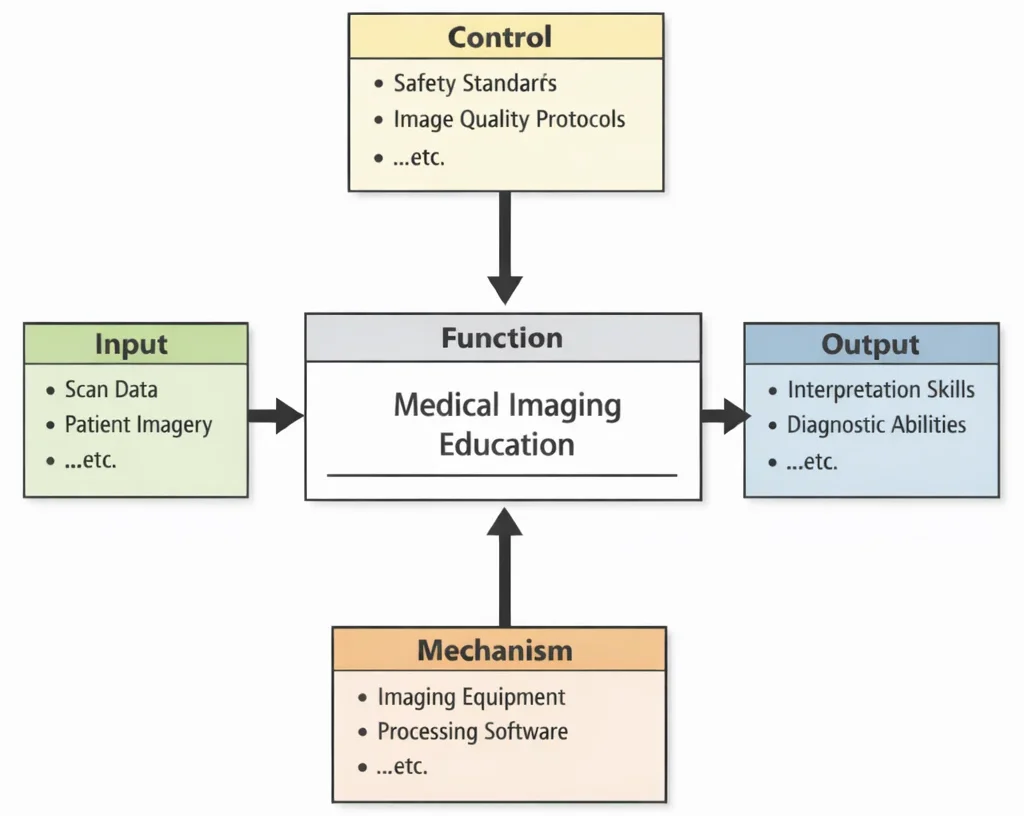
IDEF0 structural architecture of medical imaging education: multi-modal physical inputs bounded by ALARA radiation safety standards and QA protocols, operationalized via cross-sectional instrumentation and computational reconstruction to produce verified clinical diagnostic competencies.
Medical Imaging is a transformative field within modern healthcare that enables non-invasive visualization of internal anatomical structures and physiological processes. It builds on the foundation of Biomedical Engineering by merging principles from physics, computing, and clinical medicine. With tools ranging from X-rays and MRI to ultrasound and PET scans, medical imaging helps clinicians diagnose, monitor, and treat diseases more precisely and safely.
At the computational core, techniques from Bioinformatics aid in organizing and interpreting imaging data at scale, especially in genomics-driven diagnostics. The interaction between imaging devices and body tissues is heavily influenced by the use of advanced Biomaterials, which optimize compatibility and image clarity. Understanding tissue mechanics through Biomechanics further enhances image interpretation and informs device placement.
The field also benefits from innovations in Biomedical Signal Processing, where raw data from sensors is refined into high-resolution images. Specialists in Cardiovascular Engineering apply imaging to track blood flow, heart valve function, and vessel integrity in real-time. Meanwhile, clinical infrastructure supported by Clinical Engineering ensures that imaging equipment operates reliably and safely across hospital systems.
Medical imaging is integral to visualizing brain activity, where contributions from Neural Engineering are crucial in developing neuroimaging techniques such as EEG, fMRI, and MEG. The delivery and monitoring of drug interactions, guided by Pharmaceutical Engineering, often require contrast agents and real-time visualization. Additionally, advancements in Rehabilitation Engineering leverage imaging to assess musculoskeletal performance and assist in therapy planning.
Engineers in Tissue Engineering and Regenerative Medicine rely on high-resolution imaging to monitor cell growth and tissue integration. Broad engineering support comes from disciplines like Chemical Engineering, especially in developing contrast media and radiation shielding. Innovations in Biochemical Engineering further refine these imaging agents at the molecular level.
Technologies in Chemical Catalysis and Reaction Engineering contribute to real-time metabolic imaging, while Chemical Energy Systems Engineering supports power optimization in mobile imaging units. Device casings and protective components are often developed through Chemical Materials Engineering. Workflow efficiency and integration with hospital IT systems benefit from insights in Chemical Process Engineering.
Simulating image formation and optimizing detection algorithms call upon Computational Chemical Engineering. Lessons from Food and Beverage Engineering even find relevance in hygiene standards and imaging room designs. At the nanoscale, Nanotechnology in Chemical Engineering enables precision imaging using nanoparticle-based contrast agents.
Many imaging accessories, from disposable gloves to flexible sensors, are designed using principles from Polymer and Plastics Engineering. In large medical centers, Civil Engineering helps ensure that imaging rooms are built to shield radiation and vibration. Finally, in emergency and post-disaster deployments, portable imaging systems are designed using insights from Earthquake and Disaster Engineering, ensuring readiness and resilience.
Advanced multi-slice computed tomography (CT) and high-field magnetic resonance imaging (MRI) diagnostic console suite, executing real-time cross-sectional reconstruction and radiomic volumetric analysis.
Biomedical Engineering – Knowledge Map & Cluster Navigation
Explore how Medical Imaging fits within the broader Biomedical Engineering framework. This unified cluster map illustrates the strategic relationships across tissue visualization, signal processing, clinical deployment, and physiological analysis:
Medical Imaging (Current Node)
Focuses on generating and interpreting visual representations of internal anatomy and metabolic processes.
Biomedical Signal Processing
Applies mathematical reconstruction algorithms, noise filtering, and k-space transforms to construct high-resolution images.
Biomechanics
Provides motion analysis and tissue strain data captured dynamically via 4D MRI and ultrasound imaging modalities.
Biomaterials
Formulates targeted contrast agents, magnetic nanoparticles, and radiopharmaceuticals to enhance diagnostic contrast.
Tissue Engineering & Regenerative Medicine
Employs non-invasive micro-CT and MRI to monitor stem cell migration, scaffold vascularization, and tissue matrix growth.
Cardiovascular Engineering
Utilizes echocardiography, cardiac CT, and MRA to evaluate blood perfusion, coronary stenoses, and heart valve mechanics.
Neural Engineering
Relies on fMRI, PET, and MEG imaging to map cognitive brain activity, neural tracts, and neurodegenerative pathologies.
Bioinformatics
Integrates radiomic image feature extraction with genomic profiles to drive radiogenomics and targeted precision therapy.
Pharmaceutical Engineering
Tracks organ drug distribution, pharmacokinetics, and nanocarrier therapeutic release visually in real time.
Rehabilitation Engineering
Employs fluoroscopy and musculoskeletal ultrasound to evaluate post-surgical recovery and prosthetic alignment.
Clinical Engineering
Manages PACS network architecture, radiation shielding compliance, and scanner calibration QA routines across facilities.
Biomedical Engineering (Hub Overview)
Establishes the foundational multidisciplinary principles connecting physical imaging technologies to healthcare delivery.
Core Principles of Medical Imaging
1. Image Acquisition
Image acquisition is the foundational process of capturing internal anatomical or physiological data using specialized physical energy modalities:
- Projection Imaging: Traditional planar X-ray and mammography capture dense anatomical shadows, widely applied in bone fracture detection and breast cancer screening.
- Cross-Sectional Imaging:
- Computed Tomography (CT): Rotates X-ray beams and detectors to compute high-resolution 3D volume slices of head, thoracic, and abdominal structures.
- Magnetic Resonance Imaging (MRI): Utilizes powerful magnetic fields and radiofrequency pulses to align tissue hydrogen protons, yielding superior soft-tissue contrast without ionizing radiation.
- Ultrasound: Transmits high-frequency acoustic waves into tissue to map density interfaces in real time; non-ionizing, highly portable, and safe.
- Functional & Nuclear Imaging:
- Positron Emission Tomography (PET): Tracks positron-emitting radiotracers (e.g., \(^{18}\text{F-FDG}\)) to map cellular glucose metabolism in oncology and neurology.
- Single-Photon Emission Computed Tomography (SPECT): Uses gamma-emitting tracers to measure regional organ perfusion and blood flow.
2. Image Reconstruction
Reconstruction converts raw mathematical detector signals into readable spatial images:
- Filtered Back Projection (FBP): Traditional CT reconstruction method; computationally fast but prone to noise artifacts at reduced radiation doses.
- Iterative Reconstruction (IR): Refines images mathematically across iterative loops, significantly reducing image noise and allowing low-dose imaging protocols.
- Fourier Transform & k-Space: The mathematical core of MRI; maps raw frequency/phase radiofrequency signals into spatial anatomical domain coordinates.
- Compressed Sensing & AI Reconstruction: Accelerates acquisition times by reconstructing fully detailed images from undersampled data streams.
3. Image Interpretation & AI Analysis
Clinical evaluation extracts diagnostic meaning from visual data supported by modern computational tools:
- Computer-Aided Detection/Diagnosis (CAD): Diagnostic algorithms flag suspicious calcifications, pulmonary nodules, or brain hemorrhages for radiologist review.
- Radiomics: Extracts quantitative mathematical features (texture, entropy, intensity, wavelets) invisible to the naked human eye to predict tumor histology and treatment response.
4. Safety and Radiation Protection
Managing patient safety requires minimizing radiation exposure while preserving diagnostic quality:
where \(E\) is effective dose in Sieverts (\(\text{Sv}\)), \(W_T\) is the tissue weighting factor, and \(H_T\) is the equivalent organ dose.
5. Quality Assurance & Equipment Performance
Routine QA protocols ensure scanner consistency across clinical operations using calibrated phantoms, signal-to-noise ratio (SNR) measurement, spatial resolution testing, and geometric linearity verification.
Contemporary 2026 AI-Era Computational Paradigms in Medical Imaging
Modern imaging science fuses inverse problem physics with deep operator networks to drastically accelerate acquisition and enhance diagnostic fidelity:
- Physics-Informed Neural Networks (PINNs) for CT Radon Inversion: Traditional filtered back projection produces severe streaking artifacts under sparse-angle scanning. PINNs enforce the underlying linear attenuation Radon transform directly during training: $$\mathcal{L}_{\text{PINN}} = \left\| \mathcal{R}[\mu(\mathbf{x})] - p(\theta, s) \right\|^2 + \lambda_{\text{TV}} \int \|\nabla \mu(\mathbf{x})\|\,\mathrm{d}\mathbf{x} + \lambda_{\text{data}} \sum_i \left\| \mu(\mathbf{x}_i) - \mu_{\text{prior}}(\mathbf{x}_i) \right\|^2$$ where \(\mathcal{R}\) is the forward Radon projection operator, \(\mu(\mathbf{x})\) is the spatial linear attenuation coefficient field, and \(p(\theta, s)\) represents sparse sinogram detector measurements. This enables diagnostic reconstruction with up to \(80\%\) fewer angular projections, slashing patient radiation dose.
- Fourier Neural Operators (FNOs) & DeepONets for Accelerated MRI: Deep operator networks map undersampled complex \(k\)-space trajectories directly to spatial anatomical images in a zero-shot, mesh-independent manner. By learning the infinite-dimensional transform between frequency and spatial domains, FNOs reconstruct full-brain 3D MR volumes in under \(100\,\text{ms}\), enabling real-time intra-operative tracking.
- Generative Diffusion Models for Low-Count PET Denoising: Ultra-low-dose PET acquisitions suffer from severe Poisson counting noise. Guided score-based diffusion models synthesize high-count tracer distribution maps while preserving exact quantitative Standardized Uptake Values (SUV), permitting a five-fold reduction in injected radiotracer activity.
Worked Engineering Calculation: CT Hounsfield Units, Linear Attenuation & Effective Dose
Analytical Multi-Step Calculation: CT Attenuation & Stochastic Radiation Risk
Problem Formulation: An adult patient undergoes a helical thoracic Computed Tomography (CT) examination at a tube potential of \(120\,\text{kVp}\). A suspected pulmonary lesion is identified within the lung parenchyma.
- The linear attenuation coefficient of water at the effective beam energy (\(E_{\text{eff}} \approx 70\,\text{keV}\)) is \(\mu_{\text{water}} = 0.192\,\text{cm}^{-1}\). The reconstructed CT number of the lesion is measured at \(\text{HU}_{\text{lesion}} = +45\,\text{HU}\). Calculate the absolute linear attenuation coefficient of the lesion (\(\mu_{\text{lesion}}\)) in \(\text{cm}^{-1}\).
- The CT console reports a volume CT dose index \(\text{CTDI}_{\text{vol}} = 12.0\,\text{mGy}\) over an anatomical scan length \(L = 35.0\,\text{cm}\) with a helical pitch factor \(p = 1.0\). Calculate the Dose-Length Product (\(\text{DLP}\)) in \(\text{mGy}\cdot\text{cm}\).
- Using the normalized ICRP-103 chest conversion coefficient \(k_{\text{chest}} = 0.014\,\text{mSv}/(\text{mGy}\cdot\text{cm})\), calculate the effective radiation dose \(E\) in milliSieverts (\(\text{mSv}\)).
- Assuming a nominal excess lifetime stochastic cancer risk coefficient of \(r = 5.5 \times 10^{-2}\,\text{Sv}^{-1}\), calculate the individual nominal excess fatal cancer risk from this single diagnostic procedure.
Step 1: Calculate Linear Attenuation Coefficient from Hounsfield Units
The Hounsfield Unit scale is defined by:
$$\text{HU} = 1000 \times \left(\frac{\mu_{\text{tissue}} - \mu_{\text{water}}}{\mu_{\text{water}}}\right)$$
Rearranging for \(\mu_{\text{lesion}}\):
$$\mu_{\text{lesion}} = \mu_{\text{water}} \left(1 + \frac{\text{HU}_{\text{lesion}}}{1000}\right)$$
Substitute numerical values:
$$\mu_{\text{lesion}} = (0.192\,\text{cm}^{-1}) \times \left(1 + \frac{45}{1000}\right) = 0.192 \times (1 + 0.045) = 0.192 \times 1.045 = \mathbf{0.2006\,\text{cm}^{-1}}$$
Step 2: Calculate the Dose-Length Product (DLP)
$$\text{DLP} = \text{CTDI}_{\text{vol}} \times L = (12.0\,\text{mGy}) \times (35.0\,\text{cm}) = \mathbf{420.0\,\text{mGy}\cdot\text{cm}}$$
Step 3: Calculate the Effective Radiation Dose (\(E\))
$$E = \text{DLP} \times k_{\text{chest}} = (420.0\,\text{mGy}\cdot\text{cm}) \times (0.014\,\text{mSv}/(\text{mGy}\cdot\text{cm})) = \mathbf{5.88\,\text{mSv}}$$
Step 4: Compute Nominal Excess Cancer Risk
Convert effective dose to Sieverts:
$$E = 5.88\,\text{mSv} = 5.88 \times 10^{-3}\,\text{Sv}$$
$$\text{Excess Risk} = E \times r = (5.88 \times 10^{-3}\,\text{Sv}) \times (0.055\,\text{Sv}^{-1}) = 3.234 \times 10^{-4} \approx \mathbf{0.0323\%} \quad \left(\sim 1 \text{ in } 3{,}090\right)$$
Physical Interpretation & Design Implication:
The linear attenuation coefficient of \(0.2006\,\text{cm}^{-1}\) (\(+45\,\text{HU}\)) confirms a soft-tissue density consistent with a solid solitary pulmonary nodule rather than simple fluid cyst (\(0\text{--}15\,\text{HU}\)) or lipid hamartoma (\(\lt 0\,\text{HU}\)). The resulting effective dose of \(5.88\,\text{mSv}\) delivers a modest lifetime attributable stochastic cancer risk (\(\sim 1\) in \(3{,}090\)), which is clinically justified by the vital diagnostic necessity of early malignant nodule detection. Deploying iterative reconstruction (IR) or deep learning reconstruction (DLIR) could reduce \(\text{CTDI}_{\text{vol}}\) to \(\sim 4.0\,\text{mGy}\), slashing effective dose to \(1.96\,\text{mSv}\) while preserving identical spatial resolution.
Systems Engineering Trade-Off Analysis in Medical Imaging Modalities
Selecting and designing diagnostic imaging instrumentation involves balancing fundamental physical constraints across spatial resolution, temporal speed, ionizing risk, and clinical throughput:
| Imaging Modality | Primary Physical Advantage | Inherent Physical Limitation | Systems Engineering Compromise |
|---|---|---|---|
| Computed Tomography (CT) | Sub-millimeter 3D spatial resolution (\(\lt 0.5\,\text{mm}\)) and sub-second volume acquisition. | Stochastic ionizing radiation burden and poor soft-tissue contrast resolution compared to MRI. | Tube current modulation (\(\text{mAs}\)) and iterative reconstruction algorithms must balance low quantum mottle noise against cumulative patient radiation dose. |
| Magnetic Resonance Imaging (MRI) | Unrivaled soft-tissue contrast differentiation without ionizing radiation. | Prolonged acquisition times (\(20\text{--}45\,\text{min}\)), acoustic noise, and susceptibility to patient motion artifacts. | High static magnetic field strength (\(B_0 \ge 3\,\text{T}\)) boosts SNR (\(\propto B_0\)) but accelerates specific absorption rate (SAR) tissue RF heating and susceptibility distortions. |
| Diagnostic Ultrasound | Real-time hemodynamic frame rates (\(\gt 60\,\text{fps}\)), high portability, zero radiation, and low cost. | High acoustic attenuation in bone and total reflection at air interfaces; operator dependency. | Transducer acoustic frequency: high frequency (\(10\text{--}15\,\text{MHz}\)) yields sub-millimeter axial resolution but suffers high attenuation (\(\alpha \approx 0.5\,\text{dB/(cm}\cdot\text{MHz)}\)), capping penetration depth. |
| Positron Emission Tomography (PET) | Picomolar molecular sensitivity detecting cellular glucose metabolism before anatomical lesions emerge. | Poor intrinsic spatial resolution (\(4\text{--}6\,\text{mm}\)) governed by positron travel range and non-collinearity. | Requires hybrid co-registration (PET/CT or PET/MRI) to fuse functional activity onto precise anatomical frames, requiring complex dual-modality hardware alignment. |
CT Radiation Dose & Image Quality Simulator
Adjust CT scanner tube current, rotation speed, and reconstruction algorithms below to evaluate the balance between diagnostic Signal-to-Noise Ratio (SNR) and effective radiation dose (ALARA principle).
Mathematical model: Effective dose \(E \propto \text{mAs} \times (\text{kVp})^2\); Image quality \(\text{SNR} \propto \sqrt{\text{mAs}} \times \beta_{\text{recon}}\). Online interactive tool: https://prep4uni.online/stem/physical-technologies/biomedical-engineering/medical-imaging/
Major Types of Medical Imaging Technologies
X-ray Imaging
- Principle: Passes ionizing X-ray beams through body tissue; dense bone absorbs radiation (high attenuation), appearing white on film or digital detectors.
- Applications: Bone fracture diagnosis, chest radiographs (pneumonia, edema), and mammography.
- Advantages: Rapid, cheap, widely accessible.
- Limitations: Radiation exposure, poor soft-tissue contrast superposition.
Computed Tomography (CT) Scanning
- Principle: Rotates an X-ray tube and digital detector array around the patient, acquiring cross-sectional attenuation profiles reconstructed into 3D voxel matrices.
- Applications: Acute trauma, brain hemorrhages, pulmonary embolisms, tumor staging.
- Advantages: Exceptional spatial resolution, rapid acquisition speed.
- Limitations: Higher radiation exposure compared to plain X-rays.
Magnetic Resonance Imaging (MRI)
- Principle: Uses powerful superconducting magnets (\(1.5\text{--}3\,\text{T}\)) and radiofrequency pulses to manipulate hydrogen proton spin relaxation times (\(T_1, T_2\)).
- Applications: Brain, spinal cord, joint cartilage, soft-tissue tumors, cardiac anatomy.
- Advantages: Zero ionizing radiation, outstanding soft-tissue contrast.
- Limitations: Slow acquisition times, expensive, contraindicated for ferromagnetic metallic implants.
Ultrasound Imaging
- Principle: Transmits high-frequency acoustic waves (\(\gt 2\,\text{MHz}\)) via piezoelectric transducers, measuring reflected acoustic echoes from tissue interfaces.
- Applications: Obstetrics, abdominal scanning, echocardiography, point-of-care vascular checks.
- Advantages: Radiation-free, portable, real-time blood velocity doppler mapping.
- Limitations: Operator-dependent, blocked by bone and bowel air.
Positron Emission Tomography (PET)
- Principle: Injects radiotracers emitting positrons that annihilate with electrons, emitting anti-parallel \(511\,\text{keV}\) gamma photon pairs detected in coincidence circuits.
- Applications: Oncology tumor metabolic staging, cardiac viability, Alzheimer's amyloid mapping.
- Advantages: High metabolic sensitivity preceding structural anatomical changes.
- Limitations: Poor spatial resolution; requires combination with CT or MRI.
Emerging Technologies in Medical Imaging
3D and 4D Imaging
4D imaging introduces time-resolved 3D volumetric rendering, allowing real-time visualization of dynamic motion such as cardiac valve motion, fetal development, and joint biomechanics.
Molecular & Hybrid Imaging (PET/CT & PET/MRI)
Hybrid PET/CT and PET/MRI systems merge metabolic radiotracer activity with high-resolution anatomical structure in a single scan session, dramatically refining oncology staging and surgical resection planning.
Photon-Counting CT (PCCT)
Photon-counting detectors directly convert individual X-ray photons into electrical signals without energy-integrating scintillators, yielding superior spatial resolution, lower noise, and multi-energy spectral material decomposition at lower radiation doses.
AI-Powered Diagnostics & Radiomics
Deep learning networks analyze complex imaging patterns, automatically segmenting tumors, identifying acute intracranial hemorrhages, and extracting radiomic biomarkers that predict disease prognosis.
Challenges in Medical Imaging
- Radiation Exposure & Cumulative Dose: Repeated exposure to ionizing radiation during CT and fluoroscopy poses stochastic health risks. Enforcing ALARA, low-dose protocols, and dose-tracking software is critical.
- Capital Equipment Costs & Accessibility: Advanced MRI and PET/CT systems require multi-million-dollar capital outlays and specialized shielding infrastructure, limiting access in low-resource environments.
- Data Management & PACS Infrastructure: High-resolution multi-slice CT and 3D MRI sequences generate gigabytes of data per exam, demanding robust PACS network storage, DICOM interoperability, and cybersecurity safeguards.
- Radiologist Workload & Diagnostic Variability: The explosive volume of imaging studies causes burnout and inter-observer diagnostic variability, prompting the need for validated AI triage tools.
- Ethical Considerations in AI & Data Privacy: Training AI algorithms requires massive, fully anonymized imaging datasets while ensuring algorithms remain free of demographic bias.
Future Directions in Medical Imaging
- Quantum Imaging & Sensing: Leveraging quantum entanglement and hyperpolarized agents to perform ultra-sensitive MRI and low-dose molecular detection.
- Handheld Point-of-Care Ultrasound (POCUS): Single-chip ultrasound probes connecting directly to mobile devices enable bedside diagnostic scanning in ambulances, ICUs, and rural clinics.
- Radiogenomics and Personalization: Correlating imaging phenotypes with tumor genomic expression to guide personalized targeted therapy without invasive tissue biopsies.
- Wearable Continuous Imaging Sensors: Flexible adhesive ultrasound transducers offering continuous real-time blood flow and cardiac monitoring.
- Digital Twins in Surgical Planning: Fusing 3D imaging data with patient-specific CFD models to create virtual organ replicas for surgical simulation.
Why Study Medical Imaging
Non-Invasive Diagnosis and Monitoring: Medical imaging enables healthcare professionals to view internal structures without surgery. Students learn how technologies like X-rays, MRI, and ultrasound help detect disease early, improving patient outcomes through precise diagnosis and monitoring.
Understanding Imaging Modalities: Students explore the physical principles behind different imaging techniques. They study how images are produced, processed, and interpreted, providing essential foundational knowledge for advancing medical technology.
Applications Across Medical Fields: Medical imaging supports diagnosis in cardiology, oncology, orthopedics, and neurology, guiding treatment planning and surgical procedures as a cornerstone of modern medicine.
Image Analysis and Machine Learning: Students gain experience analyzing images using software and artificial intelligence, enhancing detection, automating workflows, and reducing diagnostic errors.
Ethics and Radiation Safety: The curriculum emphasizes patient safety, ethical imaging practices, and radiation protection, training students to minimize risks under regulatory guidelines.
Frequently Asked Questions
Is medical imaging painful or invasive?
Most medical imaging procedures are non-invasive and painless. You may need to lie still or receive an intravenous injection of contrast media, but staff take all measures to ensure patient comfort.
Is MRI safe, and why do some people feel anxious in the scanner?
MRI uses non-ionizing magnetic fields and radio waves, making it exceptionally safe for most patients. Anxiety usually stems from scanner noise or claustrophobia, which is managed via ear protection, open MRI designs, or mild sedation.
Why do I sometimes receive an injection of contrast before a scan?
Contrast agents (e.g., iodine for CT, gadolinium for MRI) alter attenuation or magnetic relaxation in blood vessels and tumors, sharply improving soft-tissue differentiation.
Does ultrasound use radiation?
No. Ultrasound utilizes high-frequency acoustic sound waves, completely avoiding ionizing radiation, making it ideal for obstetrics and pediatrics.
Can medical imaging replace blood tests and other investigations?
Imaging complements rather than replaces laboratory tests. Radiologists combine scan findings with blood work, histology, and clinical exams for a comprehensive diagnosis.
Will artificial intelligence replace radiologists in the future?
AI acts as an intelligent assistant—automating segmentation, flagging critical studies, and measuring lesions—while radiologists maintain ultimate clinical responsibility and patient communication.
Interactive Concept Explorations
How does k-space sampling dictate resolution and scan speed in MRI?
Why does PET imaging require coincidence detection of pair annihilation photons?
Medical Imaging Practice Module
1. Concept Foundation Questions
- What is the primary objective of medical imaging in healthcare? Answer: To non-invasively map internal anatomical structures and physiological functions to support early disease detection, therapeutic planning, surgical guidance, and monitoring.
- How does CT imaging generate 3D anatomical slices compared to projection X-rays? Answer: CT rotates an X-ray source and detector array around the body, acquiring multiple attenuation profiles reconstructed via computer algorithms into cross-sectional voxel matrices.
- What physical property enables MRI to achieve exceptional soft-tissue contrast? Answer: The manipulation of hydrogen proton nuclear spins in tissue water and fat using superconducting magnetic fields and radiofrequency pulses, measuring \(T_1\) and \(T_2\) relaxation dynamics.
- Define the ALARA principle in diagnostic radiology. Answer: ALARA stands for “As Low As Reasonably Achievable,” requiring clinicians to minimize radiation exposure via optimized scan parameters while preserving diagnostic efficacy.
- How does Doppler ultrasound measure blood flow velocity in real time? Answer: By transmitting acoustic waves and measuring the frequency shift (\(\Delta f\)) of reflected echoes from moving red blood cells, calculated via the Doppler equation.
- What radiotracer is most commonly utilized in PET cancer imaging and why? Answer: Fluorodeoxyglucose (\(^{18}\text{F-FDG}\)), because malignant cancer cells exhibit hypermetabolic glucose consumption (Warburg effect), accumulating the tracer.
- What is the main advantage of Iterative Reconstruction (IR) over Filtered Back Projection (FBP) in CT? Answer: IR reduces image noise and streak artifacts through mathematical optimization loops, allowing lower tube current (\(\text{mAs}\)) and significantly reduced radiation dose.
- Explain how contrast agents enhance diagnostic visibility in CT and MRI. Answer: CT iodine contrast increases X-ray photon attenuation; MRI gadolinium contrast shortens \(T_1\) relaxation times of nearby hydrogen protons, brightening vascularized structures.
- What defines Photon-Counting CT (PCCT) technology? Answer: PCCT uses energy-resolving semiconductor detectors that count individual X-ray photons directly, eliminating intermediate scintillation light to yield higher spatial resolution and spectral material separation.
- What role does DICOM play in medical imaging IT infrastructure? Answer: DICOM (Digital Imaging and Communications in Medicine) is the standard protocol for handling, storing, printing, and transmitting medical imaging information across PACS and EHR networks.
2. Analytical & Scenario-Based Practice
- How has the integration of artificial intelligence (AI) transformed diagnostic accuracy in medical imaging? Answer: AI deep-learning models analyze high-dimensional image data rapidly to detect subtle patterns, flag time-sensitive critical findings (e.g., stroke), and automate lesion segmentation.
- What are the ethical considerations surrounding the use of AI in medical imaging, particularly concerning patient data privacy? Answer: Key issues include ensuring patient data de-identification during training, obtaining informed consent, mitigating algorithmic demographic bias, and maintaining clear clinical accountability.
- How do different medical imaging modalities complement each other in providing a comprehensive diagnosis? Answer: Combining modalities (e.g., PET/CT or PET/MRI) fuses anatomical landmark precision with functional cellular metabolism, enabling comprehensive disease staging.
- In what ways can advancements in medical imaging reduce patient exposure to ionizing radiation? Answer: Via deep-learning image reconstruction, automatic tube current modulation, photon-counting detectors, and selecting non-ionizing alternatives (MRI/ultrasound) where applicable.
- How does the application of augmented reality (AR) in medical imaging enhance surgical planning and execution? Answer: AR projects 3D patient-specific CT/MRI segmentations directly onto the surgeon's field of view, providing real-time subsurface anatomical guidance during complex operations.
- What are the potential risks of incidental findings in full-body MRI scans, and how should they be managed? Answer: Risks include patient anxiety, overdiagnosis, and costly invasive follow-up biopsies for benign lesions. Management requires standardized clinical guidelines and clear patient communication.
- How does the use of contrast agents in imaging studies enhance diagnostic capabilities, and what are the associated risks? Answer: Contrast highlights vascularity and tissue perfusion. Risks include contrast-induced nephropathy (CIN) with iodinated agents and allergic anaphylaxis.
- How can medical imaging contribute to personalized medicine, and what challenges must be overcome to achieve this? Answer: Radiomics links imaging features to genomics to tailor therapy. Challenges include standardizing image acquisition protocols across multi-site scanners.
- What are the implications of weight bias in medical imaging, and how can healthcare systems address this issue? Answer: Weight bias causes equipment gantry size limitations and beam attenuation image degradation. Mitigation requires wide-bore scanners, high-penetration ultrasound probes, and inclusive care protocols.
- Analyze why CT is preferred over MRI in acute emergency room trauma evaluations. Answer: CT scans acquire whole-body 3D volumes in under 10 seconds, accommodate emergency life-support hardware, and excel at detecting acute bony fractures and hemorrhage.
3. Quantitative Engineering Calculations
- An ultrasound wave travels through muscle tissue at a speed of \(c = 1540\,\text{m/s}\). If a piezoelectric transducer operates at a frequency \(f = 5.0\,\text{MHz}\), calculate the acoustic wavelength \(\lambda\) (in \(\text{mm}\)) and determine the theoretical axial resolution limit (\(\lambda / 2\)).
Answer:
Wavelength \(\lambda = \frac{c}{f} = \frac{1540\,\text{m/s}}{5.0 \times 10^6\,\text{Hz}} = 0.000308\,\text{m} = \mathbf{0.308\,\text{mm}}\).
Axial Resolution Limit \(= \frac{\lambda}{2} = \frac{0.308\,\text{mm}}{2} = \mathbf{0.154\,\text{mm}}\). - A patient undergoes a CT scan with a \(\text{CTDI}_{\text{vol}}\) of \(15\,\text{mGy}\) over a scan length \(L = 40\,\text{cm}\). Calculate the Dose Length Product (\(\text{DLP}\) in \(\text{mGy}\cdot\text{cm}\)) and the total effective radiation dose \(E\) (in \(\text{mSv}\)) using a chest tissue conversion factor \(k = 0.014\,\text{mSv}/(\text{mGy}\cdot\text{cm})\).
Answer:
\(\text{DLP} = \text{CTDI}_{\text{vol}} \times L = 15\,\text{mGy} \times 40\,\text{cm} = \mathbf{600\,\text{mGy}\cdot\text{cm}}\).
Effective Dose \(E = \text{DLP} \times k = 600\,\text{mGy}\cdot\text{cm} \times 0.014\,\text{mSv}/(\text{mGy}\cdot\text{cm}) = \mathbf{8.4\,\text{mSv}}\). - In a \(1.5\,\text{Tesla}\) MRI scanner, hydrogen protons precess at a Larmor frequency governed by \(\gamma / (2\pi) = 42.58\,\text{MHz/Tesla}\). Calculate the exact resonant radiofrequency \(f_0\) (in \(\text{MHz}\)) required to induce nuclear magnetic resonance.
Answer:
Larmor equation: \(f_0 = \left(\frac{\gamma}{2\pi}\right) B_0\).
\(f_0 = 42.58\,\text{MHz/T} \times 1.5\,\text{T} = \mathbf{63.87\,\text{MHz}}\). - Calculate the Doppler frequency shift \(\Delta f\) (in \(\text{Hz}\)) for blood flowing at velocity \(v = 0.4\,\text{m/s}\) towards an ultrasound transducer operating at \(f_0 = 3.5\,\text{MHz}\), assuming speed of sound in blood \(c = 1540\,\text{m/s}\) and insonation angle \(\theta = 0^\circ\) (\(\cos 0^\circ = 1\)).
Answer:
Doppler shift formula: \(\Delta f = \frac{2 f_0 v \cos\theta}{c}\).
\(\Delta f = \frac{2 \times (3.5 \times 10^6\,\text{Hz}) \times 0.4\,\text{m/s} \times 1}{1540\,\text{m/s}} = \frac{2{,}800{,}000}{1540} \approx \mathbf{1818.18\,\text{Hz}}\) (or \(\mathbf{1.82\,\text{kHz}}\)). - A planar X-ray beam with initial intensity \(I_0\) enters a \(4.0\,\text{cm}\) thick bone tissue layer with a linear attenuation coefficient \(\mu = 0.5\,\text{cm}^{-1}\). Using Beer-Lambert's Law (\(I = I_0 e^{-\mu x}\)), calculate the percentage of initial X-ray intensity transmitted through the bone.
Answer:
Transmission ratio \(\frac{I}{I_0} = e^{-\mu x} = e^{-(0.5\,\text{cm}^{-1} \times 4.0\,\text{cm})} = e^{-2.0} \approx 0.135335\).
Transmitted intensity \(= \mathbf{13.53\%}\). - A digital radiography flat-panel detector has a pixel size of \(100\,\mu\text{m}\) (\(0.1\,\text{mm}\)). Calculate the spatial Nyquist sampling frequency limit in line pairs per millimeter (\(\text{lp/mm}\)).
Answer:
Nyquist limit \(f_{\text{Nyquist}} = \frac{1}{2 \times \text{pixel size}}\).
\(f_{\text{Nyquist}} = \frac{1}{2 \times 0.1\,\text{mm}} = \frac{1}{0.2\,\text{mm}} = \mathbf{5.0\,\text{lp/mm}}\). - In a PET scanner, a radiotracer sample has an initial activity \(A_0 = 400\,\text{MBq}\). If the radionuclide fluorine-18 has a physical half-life \(t_{1/2} = 110\,\text{minutes}\), calculate the remaining radioactive activity \(A\) (in \(\text{MBq}\)) after \(330\,\text{minutes}\).
Answer:
Number of elapsed half-lives \(n = \frac{330\,\text{min}}{110\,\text{min}} = 3\).
Remaining Activity \(A = A_0 \left(\frac{1}{2}\right)^n = 400\,\text{MBq} \times \left(\frac{1}{2}\right)^3 = \frac{400}{8} = \mathbf{50\,\text{MBq}}\).