
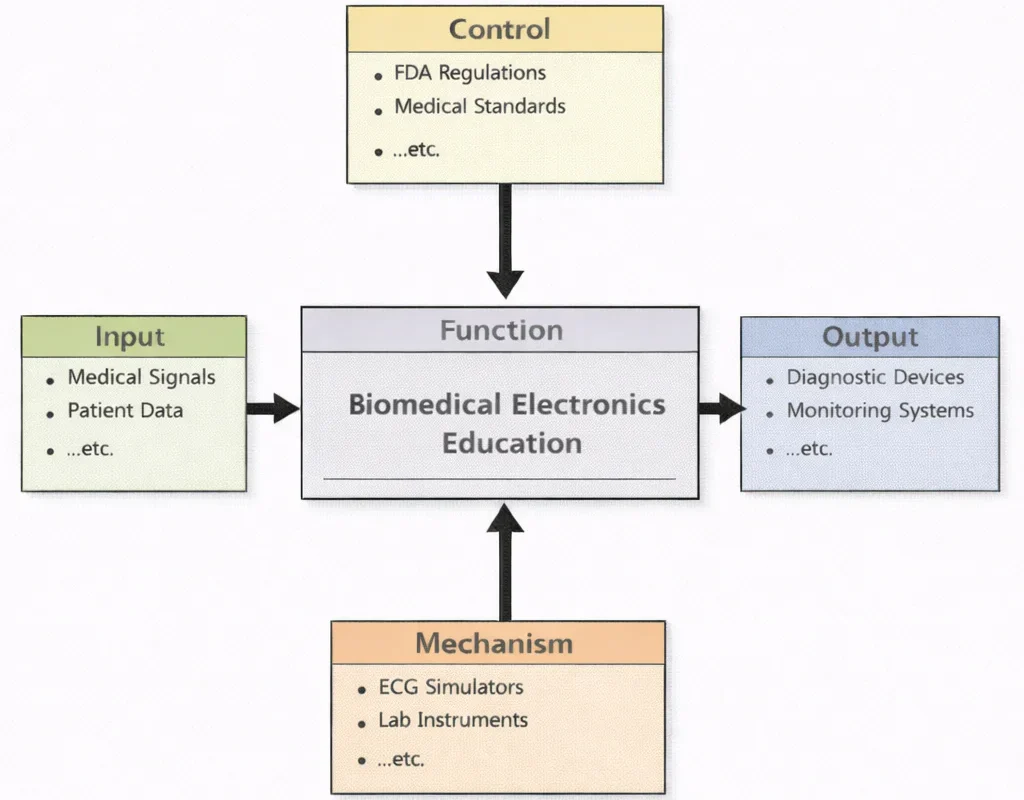
Biomedical Electronics Education, in essence, teaches students to make living systems “legible” to electronics—without losing respect for the fact that a patient is not a test bench. The diagram’s flow captures that discipline: real physiological inputs are translated into measurable, usable electrical forms; strict controls (safety, standards, ethics, and regulation) shape every design choice; and hands-on mechanisms (labs, tools, prototypes, teamwork) turn abstract theory into working practice. The output is not just the ability to wire a circuit, but the ability to build trustworthy biomedical devices—systems that acquire signals cleanly, reduce noise intelligently, protect users rigorously, and perform consistently in the messy reality of clinical environments.
Biomedical Electronics represents a transformative intersection between engineering and healthcare, offering life-enhancing solutions through innovation and precision. As a subfield of Electrical and Electronic Engineering, it harnesses principles from Electronics Engineering and advances in Embedded Systems and Microelectronics to build devices that monitor, diagnose, and treat medical conditions with remarkable accuracy.
A major area of development includes wearable and implantable devices, many of which rely on highly sensitive Instrumentation and Measurement systems. These systems, often integrated with Signal Processing algorithms, can extract critical health data from ECGs, oxygen sensors, or EEG monitors. Biomedical systems are increasingly interconnected through the Internet of Things (IoT) and Smart Technologies, enabling real-time updates to clinicians and even predictive diagnostics.
Interactive ECG Signal Conditioning & Filter Simulator
Adjust heart rate (BPM), mains interference (\(50/60\,\text{Hz}\)), and electromyographic (EMG) muscle tremor artifacts. Toggle the digital signal processing (DSP) bandpass and notch filter pipeline to observe real-time physiological signal conditioning and artifact rejection.
To maintain reliability and power autonomy, these devices benefit from research in Power Systems Engineering and the growing relevance of Renewable Energy and Energy Storage. Some implantable devices even explore the limits of miniaturized quantum effects, a field informed by Quantum Electronics. The future of assisted living and robotic surgery also lies within the reach of Robotics and Automation in E&E.
Control systems enable precision in life-support machines and prosthetic interfaces, drawing on fundamental principles from Control Systems Engineering. Furthermore, efficient communication of health metrics is critical in emergency care and telemedicine, supported by innovations in Communication Engineering.
Biomedical Electronics is also a contributor to environmentally conscious healthcare systems. Tools from Environmental Monitoring and Data Analysis help track hospital waste emissions and hygiene compliance. In line with global sustainability efforts, integration with Green Building and Sustainable Design ensures that medical facilities adopt energy-efficient systems.
Medical technology also intersects with efforts in Waste Management Engineering and Air Quality Engineering, especially in handling toxic disposables and maintaining sterile air environments. Broader policy implementation relies on Environmental Policy and Management and initiatives from Climate Change Mitigation and Adaptation.
In manufacturing, the deployment of biomedical devices depends on streamlined techniques developed in Industrial and Manufacturing Technologies. These production processes must align with the principles of Industrial Ecology and Circular Economy, ensuring safety, recyclability, and ethical sourcing. Increasingly, engineers are also partnering with specialists in Ecological Engineering to minimize ecological footprints of diagnostic equipment.
Finally, Biomedical Electronics contributes to public health resilience by supporting infrastructure in Renewable Energy Systems Engineering and ensuring water quality through Water Resources Engineering. For students preparing for university studies, this field offers a compelling mix of electrical principles, innovation, ethical responsibility, and social impact.

Biomedical Electronics: Engineering Solutions for Health and Life Sciences
Electrical & Electronic Engineering – Overview
Serves as the foundational hub anchor, detailing how high-power transmission, low-power microelectronics, and signal conditioning establish the technical roadmap across the entire cluster.
Biomedical Electronics
Focuses on the design, isolation, and clinical integration of biosensors, implantable stimulators, and diagnostic imaging circuits that directly interface with human physiological systems.
Signal Processing
Provides digital filtering, wavelets, and noise-cancellation algorithms essential for interpreting noisy bio-potentials like ECG, EEG, and EMG in clinical environments.
Instrumentation & Measurement
Covers precision transductive sensors, isolation amplifiers, and calibration standards required to safely convert physical physiological phenomena into accurate electrical data.
Electronics Engineering
Delivers discrete analog design, operational amplifier stages, and low-noise front-ends that condition weak biological micro-volt signals for downstream digital processing.
Embedded Systems & Microelectronics
Explores ultra-low-power microcontrollers, SoC architectures, and real-time firmware execution that power wearable diagnostic monitors and implantable cardiac devices.
Control Systems Engineering
Applies closed-loop feedback design to therapeutic health equipment, ensuring automated, precise delivery in mechanical ventilators, dialysis pumps, and insulin infusers.
Communication Engineering
Examines RF telemetry, Medical Implant Communication Services (MICS) bands, and encrypted telemetry pipelines for secure wireless patient data streaming.
IoT & Smart Technologies
Connects medical wearables and home sensors to cloud analytics platforms, driving the expansion of the Internet of Medical Things (IoMT) and remote patient monitoring.
Robotics & Automation in EE
Integrates precision servo control, haptic feedback, and computer vision to enable minimally invasive robotic surgical suites and active mobility exoskeletons.
Power Systems Engineering
Ensures uninterruptible, isolated electrical power architectures for hospital intensive care units, operating theaters, and emergency life-support equipment.
Renewable Energy & Energy Storage
Develops solid-state battery chemistries, inductive wireless charging, and body-heat energy harvesting to power continuous implantable medical systems.
Quantum Electronics
Explores sub-atomic spin sensors, nitrogen-vacancy diamond magnetometers, and quantum optics to revolutionize ultra-high-resolution medical imaging and diagnostics.
Core Components of Biomedical Electronics
Biomedical electronics is a multidisciplinary field that combines principles from electrical engineering, medicine, materials science, and computer science to develop devices that monitor, diagnose, treat, and even augment human physiological functions. This field serves as the foundation for technologies ranging from wearable health trackers to implantable life-saving devices. It requires precision engineering, deep understanding of biological systems, and rigorous safety compliance. The following expanded overview delves into the core components and their broader implications.
- Electronic Engineering FoundationsAdvanced sensors detect physiological parameters including heart rate, blood pressure, glucose concentration, neural spikes, and muscle activity. Engineers work on miniaturization, biocompatibility, low power consumption, and high sensitivity. Actuators convert electronic signals into therapeutic actions such as pacemakers, deep brain stimulators, and insulin pumps. Signal processing algorithms filter out artifacts and support pattern recognition, while specialized power management circuits regulate voltage for patient safety.
- Biomedical IntegrationBiocompatibility requires using inert or bioactive materials that ensure no adverse immune response or biofouling over long implantation periods. Miniaturization drives multi-layer PCB design, system-on-chip (SoC) technology, and flexible electronics to integrate comfortably with human tissue. Data communication relies on secure wireless protocols such as Bluetooth Low Energy (BLE), MICS radio bands, and NFC for continuous real-time data streaming.
- Safety and RegulationMedical devices must meet strict global standards like ISO 13485, IEC 60601, and ISO 14971 for electrical safety, electromagnetic compatibility (EMC), and risk management. Reliability engineering mandates accelerated life testing, redundancy design, and real-time fault tolerance to prevent catastrophic failures in critical life-support scenarios.
Key Technologies in Biomedical Electronics
Biomedical electronics represents a cutting-edge intersection of engineering and healthcare, delivering innovative tools that enhance diagnosis, treatment, monitoring, and rehabilitation. Engineers design systems that interface seamlessly with the human body—whether implantable, wearable, or part of a clinical workflow—offering high precision, reliability, and patient comfort. Below is a comprehensive expansion of the core technologies shaping modern biomedical electronics, highlighting their mechanisms, applications, and future trajectories.
- Implantable Medical DevicesIncludes cardiac pacemakers, implantable cardioverter defibrillators (ICDs), cochlear implants, and neurostimulators for Parkinson's disease and chronic pain management. Key Applications: Real-time cardiac rhythm correction, auditory nerve stimulation, and adaptive deep-brain neuro-modulation.
- Diagnostic and Imaging SystemsEncompasses Magnetic Resonance Imaging (MRI), Computed Tomography (CT), Electrocardiograms (ECGs), and Electroencephalograms (EEGs). Key Applications: Soft tissue mapping, rapid 3D anatomical scanning, and real-time electrophysiological bio-potential recordings.
- Wearable Health MonitorsContinuous monitoring devices such as smartwatches, continuous glucose monitors (CGMs), and cuffless blood pressure monitors. Key Applications: Outpatient health tracking, early arrhythmia detection, and real-time bio-metric cloud sync.
- Therapeutic DevicesLife-sustaining clinical platforms including hemodialysis machines, closed-loop insulin pumps, and linear accelerator radiation therapy equipment. Key Applications: Renal replacement, automated glycemic control, and targeted oncology treatment.
- Biosensors and Lab-on-a-Chip TechnologiesElectrochemical transducers and microfluidic diagnostic chips that miniaturize complex laboratory analyses. Key Applications: Rapid point-of-care pathogen testing, biomarker detection, and micro-scale blood analysis.
- Prosthetics and ExoskeletonsMyoelectric bionic limbs and powered robotic rehabilitation suits. Key Applications: Intuitive neural/muscular prosthetic motion and motorized physical therapy gait training.
- Telemedicine and Remote MonitoringWireless connected patches, smart inhalers, and cellular blood pressure units. Key Applications: Remote patient triage, chronic condition management, and virtual clinical consultation pipelines.
- Artificial Organs and Tissue EngineeringVentricular assist devices (VADs), total artificial hearts, and retinal bioelectronic implants. Key Applications: End-stage cardiac circulatory support and bio-hybrid vision restoration.
Applications of Biomedical Electronics
- CardiologyPacemakers, defibrillators, and ECG machines monitor and correct life-threatening cardiac arrhythmias, ensuring constant heart health tracking in both clinical ICUs and outpatient environments.
- NeurologyDeep brain stimulators manage motor symptoms in Parkinson's disease, while high-density EEGs and brain-computer interfaces (BCIs) allow locked-in patients to control external assistive devices.
- Diabetes ManagementContinuous glucose monitors paired with automated insulin pumps form closed-loop "artificial pancreas" systems, drastically reducing hypoglycemic risks and stabilizing blood sugar levels.
- Rehabilitation MedicineMyoelectric prosthetics read residual muscle bio-potentials for multi-axis limb control, while wearable exoskeletons provide motor assistance during spinal cord injury rehabilitation.
- Critical CareICU patient monitors, smart mechanical ventilators, and automated hemodialysis units maintain precise physiological stability in acute intensive care settings.
- Cancer TreatmentAdvanced imaging suites (PET/CT) combine with image-guided linear accelerators to target malignant tumors precisely while sparing surrounding healthy tissue.
- Public Health and WellnessConsumer health wearables aggregate broad demographic biometric trends, empowering preventive care and facilitating population-wide health studies.
- Surgical ApplicationsRobotic surgical consoles like da Vinci translate surgeon wrist movements into microscopic, steady instrument actions for minimally invasive interventions.
Contemporary Computational Paradigms in Biomedical Engineering
Modern biomedical electronics operates far beyond simple empirical thresholding. The translation of highly stochastic, non-stationary physiological signals and the physical interactions of living tissues with electromagnetic energy demand modern computational frameworks:
- Physics-Informed Neural Networks (PINNs): In cardiac electromechanics and non-invasive electrophysiological imaging, PINNs embed the Bidomain equations directly into the neural network loss function: $$\mathcal{L}_{\text{total}} = \mathcal{L}_{\text{data}} + \lambda_{\text{bio}} \left\| \nabla \cdot \left(\mathbf{\sigma}_i \nabla v_m\right) - \chi \left( C_m \frac{\partial v_m}{\partial t} + I_{\text{ion}}(v_m, \mathbf{w}) \right) \right\|^2$$ where \(v_m\) is the transmembrane potential, \(\mathbf{\sigma}_i\) is intracellular conductivity tensor, \(\chi\) is membrane surface-to-volume ratio, and \(I_{\text{ion}}\) represents nonlinear ionic currents governed by FitzHugh-Nagumo or Hodgkin-Huxley kinetics. PINNs reconstruct 3D cardiac wave-front propagation from multi-lead surface ECGs without expensive volumetric discretization.
- Fourier Neural Operators (FNOs) & DeepONets for Real-Time Thermal Dosimetry: During RF ablation and high-intensity focused ultrasound (HIFU) oncology therapy, Pennes' Bioheat Transfer Equation: $$\rho c_p \frac{\partial T}{\partial t} = \nabla \cdot (k \nabla T) + q_{\text{met}} + \omega_b c_b (T_a - T) + Q_{\text{RF}}$$ must be evaluated in real time to spare adjacent healthy nerves. FNOs learn continuous operator mappings from applied SAR power distributions \(Q_{\text{RF}}\) to dynamic 3D temperature fields \(T(\mathbf{x}, t)\), delivering millisecond-scale thermal predictions.
- Edge Invariant State Estimation & Biomechanical Kalman Filtering: In motorized exoskeletons and smart neuroprosthetics, Invariant Extended Kalman Filters (IEKF) and Unscented Kalman Filters (UKF) operate directly on low-power ARM Cortex-M or FPGA edge silicon. By leveraging \(SE(3)\) Lie group manifold geometries, these filters fuse IMU arrays and surface EMG telemetry to estimate limb kinematics and intent deterministically without drift.
- Digital Twins for In Silico Patient Modeling: Closed-loop hemodynamic digital twins synchronize real-time catheter pressure transducers and optical PPG streams to continuously estimate left-ventricular stroke work and vascular compliance, enabling automated vasoactive drug titration and predictive sepsis alerts.
Challenges in Biomedical Electronics
- Complexity of Biological Systems and Electrode-Electrolyte PhysicsHuman biological systems are dynamic, non-linear, and highly variable. Converting ionic cellular signals into electrical data requires adaptive, noise-immune sensors and sophisticated signal processing. At the biophysical electrode interface, non-polarized Ag/AgCl half-cells develop half-cell potential offsets \(V_{hc}\) and frequency-dependent Warburg impedances \(Z_W(\omega) = \frac{A_W}{\sqrt{j\omega}}\). Mechanical shear disrupts the electric double layer (Helmholtz plane), injecting massive low-frequency baseline wander that requires ultra-high common-mode rejection front-ends.
- Power and Energy Limitations in Hermetic ImplantsImplantable systems are severely constrained by battery size and replacement risks. Engineers must design ultra-low-power ASICs, efficient wireless power transfer protocols, and body-heat energy harvesting. Thermodynamic constraints limit primary cell capacity. Primary lithium-iodine (\(\text{Li-I}_2\)) and lithium carbon monofluoride (\(\text{Li-CF}_x\)) chemistries exhibit internal resistance growth over decades. Every microjoule spent in RF telemetry or active filtering directly reduces device lifespan, requiring deep sub-threshold sub-microwatt analog design.
- Biocompatibility, Fibrotic Encapsulation, and Foreign Body ResponseImplants must prevent adverse immune responses, tissue inflammation, and material corrosion over decades of exposure to body fluids. Under ISO 10993 standards, materials must resist leaching and cytotoxic responses. In vivo, macrophage activation and giant cell formation result in dense avascular collagenous encapsulation. This fibrotic sheath insulates pacing electrodes, causing pacing thresholds to rise by several volts and increasing battery drain.
- Data Security, Privacy, and IoMT Cyber-VulnerabilitiesWireless patient data pipelines and cloud IoMT connections are vulnerable to cyber threats, requiring hardware roots-of-trust, end-to-end encryption, and HIPAA/GDPR compliance. Medical devices with wireless programming ports are susceptible to replay attacks, telemetry sniffing, and unauthorized firmware modification. Hardware-enforced cryptographic boundaries, physical unclonable functions (PUFs), and anti-tamper memory enclosures are essential to prevent life-threatening interventions.
- High Development Costs and Strict Regulatory LifecyclesDesigning medical electronics takes 5 to 10 years and costs millions due to rigorous human clinical trials, bench testing, and FDA/CE regulatory reviews. Under FDA 21 CFR 820, ISO 14971 risk management, and IEC 62304 medical software life cycle standards, every revision demands formal verification and validation (V&V), exhaustive traceability matrices, and multi-center clinical trials that introduce substantial capital barriers.
- Access, Affordability, and Harsh Operating EnvironmentsHigh-tech diagnostic tools often remain out of reach for under-funded health systems in developing nations. Extreme temperatures, high humidity, unstable grid infrastructure, and lack of trained biomedical service personnel require frugal engineering: robust tropicalized circuit coatings, battery-buffered solar interfaces, and modular open-hardware diagnostic topologies.
Future Trends in Biomedical Electronics
- Edge AI and Neuromorphic Real-Time DiagnosticsEdge AI algorithms embedded directly into diagnostic chips analyze real-time ECG and EEG streams to predict acute cardiac or epileptic events hours before physical onset, bypassing the latency and privacy vulnerabilities of cloud transmission.
- Transient Bio-Resorbable and Epidermal ElectronicsFlexible, skin-conformal electronic patches and bio-resorbable sensors constructed from silk fibroin, magnesium conductors, and silicon nanomembranes dissolve naturally in physiological fluids after complete post-operative monitoring.
- Resonant Inductive Wireless Power and Deep-Tissue Ultrasound HarvestingThermoelectric, piezoelectric, and high-frequency inductive wireless power transfer eliminate physical battery replacement surgeries. Sub-millimeter ultrasound-driven "neural dust" implants harvest acoustic energy at megahertz frequencies to power localized neural recording nodes.
- Closed-Loop Personalized Pharmacotherapy & Bio-Electronic MedicineIntegration of real-time bio-sensor tracking with genomic data enables custom-tailored automated drug dosing. Vagus nerve stimulation (VNS) electronic implants modulate systemic inflammatory responses, providing electronic alternatives to pharmaceuticals for rheumatoid arthritis.
- Patient-Specific 3D Bio-Printing and Conductive Hydrogel ElectrodesPatient-matched 3D printed titanium orthopedics and conductive bio-inks accelerate custom organ repair and prosthetic fitting, eliminating impedance mismatches between rigid metal pins and soft biological matter.
- Internet of Medical Things (IoMT) and Ambient Clinical SensingUnified hospital-to-home networks automatically sync home monitoring metrics with electronic health records for proactive clinical management, utilizing zero-trust encrypted mesh communications.
- Quantum Diamond Magnetometers for Functional NeuroimagingNitrogen-vacancy (NV) center diamond magnetometers detect femtotesla-scale biomagnetic fields generated by cerebral neuronal action potentials at room temperature, eliminating the need for bulky liquid-helium-cooled SQUID MEG helmets.
Worked Numerical Application: ECG Analog Front-End & Right-Leg Drive Design
Engineering Calculation: High-CMRR Bio-Potential Front-End & RLD Gain Sizing
Problem Formulation: An active clinical ECG front-end utilizes a three-op-amp instrumentation amplifier (IA) to amplify a \(v_d = 1.2\,\text{mV}_{\text{peak}}\) cardiac signal. Surrounding mains wiring induces an open-circuit displacement current \(i_{\text{disp}} = 0.5\,\mu\text{A}_{\text{rms}}\) into the patient's body. The skin-electrode interface impedance to earth ground on the reference lead is \(R_G = 50\,\text{k}\Omega\). The front-end incorporates an active Right-Leg Drive (RLD) circuit with feedback resistor \(R_f = 470\,\text{k}\Omega\) and summing resistors \(R_{\text{in}} = 22\,\text{k}\Omega\). The instrumentation amplifier is configured with a differential gain \(A_d = 500\) and has an intrinsic common-mode rejection ratio \(\text{CMRR}_{\text{amp}} = 90\,\text{dB}\).
Analytical Derivation & Step-by-Step Calculations:
Step 1: Calculate the Common-Mode Voltage Without Active RLD (\(V_{\text{cm,uncompensated}}\)):
With passive grounding, the entire displacement current flows through the ground electrode impedance \(R_G\):
$$V_{\text{cm,uncompensated}} = i_{\text{disp}} \times R_G = (0.5 \times 10^{-6}\,\text{A}) \times (50 \times 10^3\,\Omega) = \mathbf{0.025\,\text{V}_{\text{rms}}}\quad (25.0\,\text{mV}_{\text{rms}})$$Step 2: Determine RLD Loop Gain (\(A_{\text{RLD}}\)) and Reduced Common-Mode Potential (\(V_{\text{cm,RLD}}\)):
The RLD inverting amplifier senses the average common-mode potential through two parallel summing resistors \(R_{\text{in}}\), yielding an effective resistance \(R_{\text{eff}} = R_{\text{in}}/2 = 11\,\text{k}\Omega\). The RLD amplifier gain is:
$$A_{\text{RLD}} = \frac{2 R_f}{R_{\text{in}}} = \frac{2 \times 470 \times 10^3}{22 \times 10^3} = \frac{940}{22} \approx \mathbf{42.73}$$With active negative feedback driving the patient's right leg, the effective body ground impedance is divided by \((1 + A_{\text{RLD}})\):
$$V_{\text{cm,RLD}} = \frac{V_{\text{cm,uncompensated}}}{1 + A_{\text{RLD}}} = \frac{0.025\,\text{V}}{1 + 42.73} = \frac{0.025}{43.73} \approx 5.717 \times 10^{-4}\,\text{V}_{\text{rms}} = \mathbf{0.572\,\text{mV}_{\text{rms}}}$$Step 3: Evaluate Output Differential Signal and Common-Mode Noise Interference:
The output differential signal voltage is:
$$V_{\text{out,sig}} = A_d \times v_d = 500 \times 1.2\,\text{mV} = \mathbf{600.0\,\text{mV}}\quad (0.60\,\text{V}_{\text{peak}})$$Convert \(\text{CMRR} = 90\,\text{dB}\) to its absolute linear ratio \(K_{\text{CMRR}}\):
$$K_{\text{CMRR}} = 10^{\frac{90}{20}} = 10^{4.5} \approx 31\,622.77$$The common-mode gain of the instrumentation amplifier is:
$$A_{\text{cm}} = \frac{A_d}{K_{\text{CMRR}}} = \frac{500}{31\,622.77} \approx \mathbf{0.01581}$$The resulting output common-mode noise voltage with RLD active is:
$$V_{\text{out,cm}} = A_{\text{cm}} \times V_{\text{cm,RLD}} = 0.01581 \times (0.5717\,\text{mV}_{\text{rms}}) \approx \mathbf{0.00904\,\text{mV}_{\text{rms}}}\quad (\mathbf{9.04\,\mu\text{V}_{\text{rms}}})$$Physical & Clinical Interpretation: Without the active RLD loop, the output common-mode noise would have been \(0.01581 \times 25\,\text{mV} = 0.395\,\text{mV}_{\text{rms}}\) (\(559\,\mu\text{V}_{\text{peak}}\)), severely contaminating the \(600\,\text{mV}_{\text{peak}}\) desired ECG output with a noticeable \(50\,\text{Hz}\) hum. The active RLD attenuation suppresses output noise down to \(9.04\,\mu\text{V}_{\text{rms}}\), yielding a pristine clinical Signal-to-Noise Ratio (SNR) exceeding \(42\,\text{dB}\) and preventing erroneous arrhythmia triggers.
Systems Engineering Architecture: Trade-Off Analysis
Developing clinical biomedical instrumentation requires managing severe multi-domain trade-offs between biological safety, physical invasiveness, battery autonomy, and regulatory risk. The following matrix illustrates the primary architectural balances:
| Design Domain | Primary Architectural Dilemma | Clinical Advantages (+) | Engineering Penalties (−) | System Mitigation Strategy |
|---|---|---|---|---|
| Bio-Potential Acquisition | Wet Ag/AgCl Gel Electrodes vs. Capacitive Dry Electrodes | Low baseline source impedance (\(\lt 5\,\text{k}\Omega\)), minimal motion artifact, established clinical standard. | Electrolytic gel desiccates over multi-day wear, causes skin erythema, poor patient compliance. | Active guard-shielded ultra-high input impedance (\(\gt 10\,\text{G}\Omega\)) bootstrapped CMOS buffers. |
| Patient Electrical Isolation | Optocoupler Isolation vs. Digital Giant Magnetoresistive (GMR) Isolators | Immune to strong magnetic fields, zero magnetic signature inside MRI suites. | High LED current consumption (\(\gt 5\,\text{mA}\)), limited transfer bandwidth, thermal degradation. | RF capacitive or micro-transformer digital isolators with duty-cycled power gating. |
| Wireless Telemetry | MICS Band (402–405 MHz) vs. 2.4 GHz Bluetooth Low Energy (BLE) | Superior human tissue penetration, minimal RF absorption, dedicated medical spectrum. | Requires proprietary base stations, lower data bitrate (\(\lt 400\,\text{kbps}\)), higher antenna geometry. | Dual-mode transceivers utilizing MICS for critical implant links and BLE for external relaying. |
| Implantable Power Delivery | Hermetic Primary Battery vs. Transcutaneous Inductive Recharging | Zero patient maintenance, no external charging hardware, complete hermetic security. | Finite operating lifespan (8–10 years), mandatory revision surgery upon exhaustion. | Resonant Class-E inductive power transfer with sub-dermal SAR thermal monitoring circuits. |
Why Study Biomedical Electronics
Biomedical Electronics: Conclusion
Biomedical electronics stands at the vital convergence of electrical engineering and medical science. By transforming subtle biological phenomena into clear, actionable electronic data, it empowers clinicians, improves patient autonomy, and revolutionizes healthcare delivery worldwide. As bio-compatible materials, low-power embedded chips, and artificial intelligence continue to evolve, biomedical electronics will remain a central pillar of global medical innovation.
Frequently Asked Questions
1. What does “biomedical electronics” actually cover?
Biomedical electronics covers the design of electronic circuits, sensors and systems that interact with the human body. This ranges from simple ECG amplifiers and pulse oximeters to complex medical imaging equipment, implantable pacemakers and wearable health trackers.
2. How is biomedical electronics different from general consumer electronics?
Consumer electronics focus on cost, performance and user experience, whereas biomedical electronics must also satisfy strict safety, reliability and regulatory constraints. Devices must be safe in contact with the body, robust against failure and accurate enough to support clinical decisions.
3. Why are biosensors so central to biomedical devices?
Biosensors translate chemical or biological quantities, such as blood glucose or oxygen saturation, into electrical signals. Without this translation, it would be impossible for electronic systems to “see” what is happening inside the body in real time.
4. What kinds of signals are processed in biomedical electronics?
Common signals include electrical activity from the heart (ECG), brain (EEG) and muscles (EMG), as well as optical, pressure and chemical signals from imaging or blood-chemistry measurements. Each type of signal requires specific conditioning and analysis techniques.
5. Why is low power consumption such a big issue for medical devices?
Many biomedical devices are battery-powered, either as wearables or implants. Low power consumption extends battery life, reduces the frequency of surgeries for implant replacement and allows small, comfortable designs that patients are more willing to use.
6. Are wearable health gadgets and hospital equipment based on similar principles?
Yes. Both rely on sensors, amplifiers, filters, microcontrollers and wireless communication. The main differences lie in performance requirements, data accuracy, robustness and how strictly the devices are regulated for clinical use.
7. How does biomedical electronics support telemedicine and remote care?
Home-based sensors, smart patches and wearable monitors can continuously collect data and send it to healthcare providers. This supports remote diagnosis, chronic disease management and early detection of problems without frequent clinic visits.
8. What career paths are open to students who study biomedical electronics?
Graduates can work in medical device design, hospital equipment support, regulatory compliance, health-tech startups, rehabilitation technology, imaging system development and research labs focused on new diagnostic or therapeutic technologies.
9. Do I need a strong biology background to succeed in biomedical electronics?
A basic understanding of human physiology is helpful, but the core skills are in circuits, signal processing, embedded systems and systems engineering. You can gradually build your biomedical knowledge while applying engineering tools to real healthcare problems.
10. How is AI starting to influence biomedical electronic systems?
AI algorithms are increasingly embedded in medical devices and cloud platforms to interpret complex signals, detect abnormal patterns and support clinical decision-making. This can make diagnostics faster, more consistent and more personalised for each patient.
Section 1: Foundational Review Questions with Answers
1. What is biomedical electronics, and how does it differ from conventional electronics?
Answer: Biomedical electronics is the application of electronic engineering principles to the design and development of medical devices and systems that diagnose, monitor, or treat health conditions. Unlike conventional electronics, which focus on consumer or industrial tasks, biomedical electronics must satisfy stricter requirements for patient safety, biocompatibility, electrical isolation, signal accuracy, reliability, sterilization, and regulatory compliance.
2. How do biosensors and transducers enable the monitoring of physiological signals?
Answer: Biosensors and transducers convert biological or chemical information into measurable electrical signals. A biosensor uses a selective sensing element (e.g., an enzyme or antibody) that interacts with a target biomarker, while the transducer converts that interaction into a voltage, current, or impedance signal for filtering and digital analysis.
3. In what ways do electronic circuits underpin medical imaging technologies such as MRI and ultrasound?
Answer: Medical imaging systems rely on electronics for signal generation, detection, amplification, filtering, and image reconstruction. In MRI, high-precision electronic timing controls gradient coils and RF pulses, while ultra-sensitive receiver circuits capture weak nuclear relaxation signals. In ultrasound, piezoelectric transducers convert electrical pulses into sound waves and transform returning echoes back into high-resolution images.
4. Why is signal processing a critical step in analysing biomedical data such as ECG or EEG recordings?
Answer: Raw biological signals contain severe noise and artifacts caused by muscle movement, skin-electrode impedance shifts, and 50/60 Hz powerline interference. Signal processing cleans the raw bio-potentials using bandpass and notch filters, isolating clinical features like QRS complexes or neural brainwave spikes for accurate diagnostic interpretation.
5. What are some key design considerations for implantable medical devices like pacemakers?
Answer: Design priorities include biocompatible hermetic encapsulation, ultra-low-power ASIC operation for long battery life, miniaturization, accurate sensing, dependable pacing outputs, and protection against electromagnetic interference (EMI). Devices must operate with total reliability inside chemical body environments without fail.
6. How do wearable health monitors balance user comfort, battery efficiency, and reliable data collection?
Answer: Designers use flexible circuits, soft bio-compatible polymers, and lightweight form factors to ensure comfort. Battery efficiency is maximized using duty-cycled low-power microcontrollers and Bluetooth Low Energy (BLE), while motion-artifact rejection algorithms ensure clinical signal accuracy during active movement.
7. Why are safety and regulatory compliance paramount in biomedical electronic systems?
Answer: Because medical devices directly contact or regulate human life, device failures or current leaks can cause fatal injuries. Regulatory compliance (such as FDA 510(k) or CE mark) ensures rigorous testing under IEC 60601 standards for electrical isolation, risk management, and failure-mode redundancy.
8. How do telemedicine and remote patient monitoring make use of biomedical electronics?
Answer: Remote monitoring relies on home-based biosensors, smart patches, and multi-sensor wearables that record vital metrics locally and transmit encrypted data to healthcare providers via wireless gateways. This enables real-time clinical alerts, proactive chronic disease management, and reduced emergency room readmissions.
9. What role do microcontrollers and embedded systems play in advanced diagnostic and therapeutic devices?
Answer: Microcontrollers act as the core logic engine, executing real-time DSP algorithms, managing sensor sampling, controlling motor/actuation drivers in infusion pumps, driving user displays, and maintaining safety interlocks in compact, energy-efficient form factors.
10. What emerging trends are likely to shape the future of biomedical electronics?
Answer: Key emerging trends include stretchable/epidermal electronics, edge AI diagnostic inferencing, bio-resorbable transient sensors, wireless inductive energy harvesting, and high-density neural interfaces for mind-controlled prosthetic limbs.
Section 2: Analytical & Scenario-Based Inquiry
1. How does understanding electrical isolation prevent microshock hazards in clinical environments?
In clinical settings, patients connected to internal catheters or cardiac leads are extremely vulnerable to microshock—where leakage currents as low as \(10\,\mu\text{A}\) direct to the heart can trigger ventricular fibrillation. Biomedical engineers utilize isolation transformers, optocouplers, and floating patient-applied parts (Type CF ratings) under IEC 60601 standards to galvanically isolate the patient from mains power ground loops, eliminating stray leakage pathways.
2. Why is motion artifact reduction a central challenge in photoplethysmography (PPG) pulse oximeters?
PPG sensors measure arterial blood volume fluctuations by detecting light absorption changes through tissue. When a patient moves, mechanical displacement between the optical sensor and skin creates massive signal fluctuations that dwarf the faint cardiac absorption pulse. Engineers overcome this using dual-wavelength differential sensing, integrated MEMS accelerometers, and adaptive LMS filtering to subtract motion noise from the optical signal stream in real time.
3. How do closed-loop feedback algorithms transform passive medical monitors into active artificial pancreas devices?
Passive continuous glucose monitors merely record interstitial sugar levels and output alarms. By integrating a continuous bio-sensor with a micro-infusion insulin pump via a proportional-integral-derivative (PID) or model predictive control (MPC) algorithm, the system continuously calculates dynamic insulin requirements. This closed-loop control automatically adjusts basal drug delivery to counteract glucose spikes and prevent nocturnal hypoglycemia without manual user intervention.
4. What trade-offs must be managed when implementing wireless power transfer for sub-dermal neurostimulators?
Inductive wireless charging eliminates the need for repeated surgical battery replacements, but high-frequency electromagnetic fields can induce tissue heating (specific absorption rate limits). Engineers balance resonant frequency selection (typically 13.56 MHz or sub-MHz bands), coil alignment tolerance, thermal monitoring sensors, and power transfer efficiency to recharge sub-dermal implants safely without causing tissue thermal damage.
5. How does right-leg drive (RLD) active grounding improve common-mode rejection in multi-lead ECG systems?
Human bodies act as antennas picking up 50/60 Hz common-mode electromagnetic noise from surrounding mains wiring. A standard differential amplifier may saturate under high common-mode voltages. Right-leg drive circuitry senses the common-mode voltage from the sensing leads, inverts it through an operational amplifier, and feeds it back into the patient's right leg, actively canceling common-mode interference and dramatically improving the overall Common-Mode Rejection Ratio (CMRR).
6. In what ways do bio-compatible titanium and PEEK materials prevent long-term implant encapsulation failure?
When foreign materials are implanted, the immune response forms a thick fibrous capsule around the device, insulating electrodes and disrupting signal sensing or electrical pacing. Using bio-inert titanium enclosures and Polyether ether ketone (PEEK) polymers, along with micro-textured bio-surfaces, minimizes foreign body inflammatory responses, preserving electrical contact resistance over multi-year implantation timelines.
7. How does myoelectric signal processing allow upper-limb amputees to control multi-articulating bionic hands?
When an amputee attempts to flex missing fingers, residual forearm muscles generate micro-volt electrical signals (EMG). Surface electrodes capture these raw muscle signals, which are amplified, rectified, and evaluated by machine learning pattern-recognition microprocessors. The system translates specific muscle contraction patterns into individual motorized finger movements, enabling fluid grip selection.
8. Why is thermal management critical in high-density integrated medical implants?
Brain tissues and delicate internal organs can suffer irreversible cellular damage if local temperatures rise by more than 1°C. As microprocessors inside neural stimulators or cochlear implants increase processing speed, power dissipation increases. Biomedical engineers utilize ultra-low-power sleep cycles, thermal-spreading ceramic packaging, and efficient clock-gating to prevent localized tissue overheating.
9. How do microfluidic lab-on-a-chip cartridges achieve rapid blood testing at the patient bedside?
Lab-on-a-chip devices utilize micro-capillary channels, electro-wetting pumps, and integrated biosensor arrays to manipulate microliter drops of blood. By integrating capillary fluidics directly over electrochemical detection pads, the chip performs cell separation, reagent mixing, and biomarker measurement in minutes, replacing centralized pathology laboratories for time-critical cardiac troponin or sepsis screening.
10. What ethical considerations govern edge AI decision-making in autonomous defibrillators?
When an ICD automatically decides to deliver a painful high-voltage shock to terminate a suspected fatal arrhythmia, false positives inflict severe psychological trauma, while false negatives cause sudden cardiac death. Engineers must ensure deterministic algorithm safety bounds, transparent decision thresholds, extensive validation across multi-ethnic bio-banks, and strict fail-safe overrides to balance speed with clinical accuracy.
11. How do zero-trust cybersecurity frameworks protect connected pacemakers from wireless exploitation?
Connected pacemakers feature telemetry for remote physician updates, creating potential attack vectors for unauthorized command injection. Implementing zero-trust security involves hardware-enforced AES-128 cryptographic keys, public-key infrastructure (PKI) mutual authentication between programmer tools and implant, anti-rollback firmware protections, and disabling unauthenticated telemetry once initial clinical sessions end.
12. How does cross-disciplinary collaboration between biophysicists and circuit designers drive bionic vision implants?
Developing retinal implants requires biophysicists to map neural optical response patterns, materials scientists to engineer flexible micro-electrode arrays that attach to optic nerves, and electronic engineers to build sub-miniature camera processing units that wirelessly transmit power and data pulses to the array. Only joint collaboration enables functional visual phosphene restoration in blind patients.
Section 3: Numerical Problems with Solutions
1. An instrumentation amplifier for an ECG circuit has a differential gain \(A_d = 1000\) and a Common-Mode Rejection Ratio (CMRR) of \(80\,\text{dB}\). If a common-mode noise voltage \(V_{\text{cm}} = 0.5\,\text{V}\) is present alongside a \(1\,\text{mV}\) peak differential ECG signal, calculate the common-mode gain (\(A_{\text{cm}}\)) and the output noise voltage (\(V_{\text{out,cm}}\)).
Solution:
CMRR in decibels is defined as:
$$\text{CMRR}_{\text{dB}} = 20 \log_{10}\left(\frac{A_d}{A_{\text{cm}}}\right)$$
Substituting the given parameters:
$$80 = 20 \log_{10}\left(\frac{1000}{A_{\text{cm}}}\right) \quad \Rightarrow \quad 4 = \log_{10}\left(\frac{1000}{A_{\text{cm}}}\right)$$
$$\frac{1000}{A_{\text{cm}}} = 10^4 = 10\,000 \quad \Rightarrow \quad A_{\text{cm}} = \frac{1000}{10\,000} = \mathbf{0.1}$$
The output common-mode noise voltage:
$$V_{\text{out,cm}} = V_{\text{cm}} \times A_{\text{cm}} = 0.5\,\text{V} \times 0.1 = \mathbf{0.05\,\text{V}}\quad (50.0\,\text{mV})$$
The amplified differential cardiac output is \(V_{\text{out,sig}} = 1\,\text{mV} \times 1000 = \mathbf{1.0\,\text{V}}\).
2. An implantable cardiac pacemaker operates continuously on a \(3.2\,\text{V}\) lithium carbon monofluoride primary battery rated at \(1.2\,\text{Ah}\). If the pacemaker draws a constant average quiescent current of \(15\,\mu\text{A}\), calculate the expected battery operational lifespan in years.
Solution:
Convert battery capacity into microampere-hours:
$$C_{\text{bat}} = 1.2\,\text{Ah} = 1\,200\,000\,\mu\text{Ah}$$
Operational lifespan in hours:
$$T_{\text{hours}} = \frac{C_{\text{bat}}}{I_{\text{avg}}} = \frac{1\,200\,000\,\mu\text{Ah}}{15\,\mu\text{A}} = 80\,000\,\text{hours}$$
Converting hours into Julian calendar years (\(365.25\,\text{days/year}\)):
$$T_{\text{years}} = \frac{80\,000\,\text{hours}}{24 \times 365.25\,\text{hours/year}} = \frac{80\,000}{8766} \approx \mathbf{9.13\,\text{years}}$$
3. A pulse oximeter measures light absorption at \(660\,\text{nm}\) (red) and \(940\,\text{nm}\) (infrared). The normalized ratio of ratios (\(R\)) is measured as \(0.70\). Using the empirical calibration formula \(\text{SpO}_2 = 110 - 25 \times R\), calculate the estimated arterial oxygen saturation percentage.
Solution:
Substitute \(R = 0.70\) directly into the empirical calibration equation:
$$\text{SpO}_2 = 110 - (25 \times 0.70) = 110 - 17.5 = \mathbf{92.5\%}$$
The arterial oxygen saturation level is **92.5%**.
4. An active bio-potential bandpass filter for an Electromyogram (EMG) amplifier requires a lower cutoff frequency \(f_L = 20\,\text{Hz}\) and an upper cutoff frequency \(f_H = 500\,\text{Hz}\). If the high-pass section uses a \(100\,\text{nF}\) capacitor, calculate the required resistance (\(R_{\text{HP}}\)) and the filter bandwidth (\(\Delta f\)).
Solution:
The high-pass pole frequency is defined by:
$$f_L = \frac{1}{2\pi R_{\text{HP}} C} \quad \Rightarrow \quad R_{\text{HP}} = \frac{1}{2\pi f_L C}$$
Evaluating numerically:
$$R_{\text{HP}} = \frac{1}{2\pi \times 20\,\text{Hz} \times (100 \times 10^{-9}\,\text{F})} = \frac{1}{1.2566 \times 10^{-5}} \approx \mathbf{79\,577.47\,\Omega}\quad (79.58\,\text{k}\Omega)$$
Total passband bandwidth:
$$\Delta f = f_H - f_L = 500\,\text{Hz} - 20\,\text{Hz} = \mathbf{480.0\,\text{Hz}}$$
5. A high-resolution \(16\)-bit Analog-to-Digital Converter (ADC) with a full-scale reference range of \(0\) to \(3.3\,\text{V}\) is used to digitize an amplified EEG signal. Calculate the voltage resolution per LSB (Least Significant Bit) in microvolts (\(\mu\text{V}\)).
Solution:
The total discrete quantization intervals for an \(N = 16\) bit converter:
$$2^N = 2^{16} = 65\,536$$
The voltage step per least significant bit:
$$\Delta V_{\text{LSB}} = \frac{V_{\text{ref}}}{2^N} = \frac{3.3\,\text{V}}{65\,536} \approx 5.0354 \times 10^{-5}\,\text{V} = \mathbf{50.35\,\mu\text{V/step}}$$
6. An ultrasonic blood flow meter utilizes the Doppler shift frequency formula \(\Delta f = \frac{2 f_0 v \cos(\theta)}{c}\). Given a transducer carrier frequency \(f_0 = 5\,\text{MHz}\), acoustic propagation velocity in soft tissue \(c = 1540\,\text{m/s}\), Doppler insonation angle \(\theta = 45^\circ\) (\(\cos(45^\circ) = 0.7071\)), and a measured Doppler shift \(\Delta f = 3.2\,\text{kHz}\), calculate the blood flow velocity (\(v\)) in m/s.
Solution:
Rearranging the continuous-wave Doppler equation for flow velocity \(v\):
$$v = \frac{\Delta f \times c}{2 f_0 \cos(\theta)}$$
Substituting the empirical clinical parameters:
$$v = \frac{(3.2 \times 10^3\,\text{Hz}) \times (1540\,\text{m/s})}{2 \times (5 \times 10^6\,\text{Hz}) \times 0.7071} = \frac{4\,928\,000}{7\,071\,000} \approx \mathbf{0.697\,\text{m/s}}\quad (69.7\,\text{cm/s})$$
7. A continuous glucose monitor (CGM) samples biosensor readings every \(5\) minutes and streams a \(32\)-byte payload per transmission over Bluetooth Low Energy. Calculate the total daily data payload transmitted in kilobytes (KB) and the average transmission bitrate in bits per second (bps).
Solution:
Number of transmissions per hour:
$$N_{\text{hour}} = \frac{60\,\text{min}}{5\,\text{min}} = 12\,\text{readings/hour}$$
Total daily transmissions:
$$N_{\text{day}} = 12 \times 24 = 288\,\text{readings/day}$$
Total daily payload volume:
$$\text{Payload} = 288 \times 32\,\text{bytes} = 9216\,\text{bytes} = \mathbf{9.216\,\text{KB}}$$
Average daily bit rate across \(24\,\text{hours}\) (\(86\,400\,\text{seconds}\)):
$$R_{\text{bit}} = \frac{9216\,\text{bytes} \times 8\,\text{bits/byte}}{86\,400\,\text{s}} = \frac{73\,728\,\text{bits}}{86\,400\,\text{s}} \approx \mathbf{0.853\,\text{bps}}$$